
Los beneficios de la lactancia materna para el lactante y la madre, su familia, el sistema sanitario y la sociedad en general están muy bien documentados en múltiples publicaciones. Por esta razón, suprimir la lactancia sin un motivo importante supone un riesgo innecesario para la salud.
Más del 90% de mujeres toman medicamentos durante el periodo de lactancia, con frecuencia dejan de dar el pecho por este motivo pese a no estar fundamentado su peligro real más que en un pequeño porcentaje de productos.
No es raro que el profesional sanitario o la madre lactante se enfrenten a la necesidad de prescribir o tomar un antidepresivo, un antibiótico, a una anestesia local para un procedimiento dental, o a la práctica de una radiografía de tórax o de una gammagrafía renal, por ejemplo.
Los profesionales afrontamos a estas cuestiones con información escasa, dispersa y contradictoria. En el Vademécum, libro que recoge fichas técnicas y prospectos de los medicamentos, la recomendación más habitual es suspender la lactancia o no tomar el medicamento en caso de lactancia sin argumentar nada o, como mucho, que el medicamento pasa a la leche. Pueden estar unidos los apartados “Embarazo” y “Lactancia” cuando nada tiene que ver el potencial teratógeno de un medicamento con un posible efecto secundario a un lactante, y la información no se corresponde con la publicada por autores y entidades de prestigio. Como veremos, el mensaje debería ser que, entre lactancia y medicamentos, una compatibilidad es casi siempre posible (Hale 2019, Patricio-Talayero 2020).
Cada vez más mujeres defienden su lactancia, constatan información contradictoria entre el prospecto del medicamento, las instrucciones del médico que prescribe y los consejos de guías, manuales de lactancia o Internet, pidiendo una respuesta clara y bien documentada.
Aunque, debido a la sobrecarga asistencial, lo que necesitamos los profesionales sanitarios son listados (véanse Tablas 1 y 2) o bases de datos (p. ej. www.elactancia.org) que nos indiquen de manera rápida y clara si una sustancia es compatible con la lactancia; es preciso conocer unas bases teóricas mínimas para decidir con conocimiento de causa, discernir entre informaciones contradictorias, poder informar adecuadamente y resolver las dudas o reticencias de madres o profesionales sanitarios.
Vamos a ver algunos datos de Farmacocinética de la lactancia, es decir, de cómo un fármaco o cualquier sustancia entra, se distribuye y se elimina de nuestro organismo, con especial atención a cómo puede llegar a excretarse en la leche materna.
Toxicidad farmacológica Mediada Por La Leche Materna
Para que una sustancia tomada por o aplicada a la madre afecte al lactante debe, o inhibir la producción de leche, o seguir todos y cada uno de los siguientes pasos:
- Pasar a sangre de la madre: La biodisponibilidad es el porcentaje de una sustancia que alcanza la circulación sistémica tras su administración, absorción intestinal y posible primera metabolización hepática. Una sustancia para llegar a la leche materna debe haber llegado primero a la sangre, al plasma, pues la leche es un filtrado del plasma sanguíneo elaborado por el lactocito alveolar mamario. Por esta razón, aquella medicación de administración tópica (cremas, ungüentos, colirios, gotas óticas, etc.) o inhalada para asma o rinitis (broncodilatadores, corticoides), muchos antiácidos y algunos laxantes, antiparasitarios intestinales y antibióticos (p.ej. los amino glucósidos) no alcanzan concentraciones en sangre materna por falta de suficiente absorción.
- Pasar a leche de la madre: Una vez en el plasma sanguíneo, las diversas moléculas pueden atravesar el epitelio alveolar mamario, sea a través de las células cubicas o entre las mismas, y llegar a la leche. El Índice Leche/Plasma es la relación de la concentración de una sustancia en la leche respecto a la concentración en plasma. Cuanto menor es esta relación (<1) menos concentración alcanza el medicamento en leche materna. Varios AINES (ibuprofeno y otros), betalactámicos, corticoides, varios hipotensores IECA (captopril, quinapril), el zafirlucast y algunas benzodiazepinas sedantes están por debajo de 0,25 y son compatibles con la lactancia.
El paso a leche depende de varias características farmacocinéticas:
I. Porcentaje de fijación de la sustancia a las proteínas plasmáticas. A mayor fijación (por encima del 80 % - 85 %) más dificultad de paso a leche, como por ejemplo la mayoría de los antidepresivos inhibidores de la recaptación de serotonina, diclofenaco, eritromicina, fenitoína, haloperidol, heparina, ibuprofeno, ketorolaco, midazolam, nedocromilo, nifedipino, propanolol, quinina o verapamilo.
II. Las sustancias de peso molecular mayor de 500 – 1.000 Dalton apenas pasan a la leche y es ínfimo o nulo el paso de macromoléculas como contrastes radiológicos, glucopéptidos, glucósidos digitálicos, heparinas, hormonas, interferones, macrólidos, miorrelajantes, anticuerpos monoclonales o rifampicina, por ejemplo.
III. A mayor liposolubilidad de una sustancia hay mayor paso a leche materna. El aumento de la ionización y la menor liposolubilidad consecuente de las sustancias acidas en un plasma discretamente menos acido (pH 7,4) que la leche (pH 7,1-7,2) dificulta su paso a leche porque las barreras celulares son más permeables a formas no ionizadas más liposolubles. Podemos tener una referencia a través de la pKa o logaritmo de la constante de disociación o ionización acida o constante de acidez (Ka). Las sustancias con pKa < 7 son de carácter ácido y, contrariamente, las de pKa > 7 son de carácter básico y tienden a acumularse en la leche ya que en este medio están más ionizadas.
IV. Volúmenes de distribución elevados se acompañan de menor paso a leche. El Volumen de distribución refleja la distribución de un medicamento en todo el cuerpo tras la administración por vía oral o parenteral. Volúmenes de distribución elevados se acompañan de menor paso a la leche por haber difundido al liquido intersticial (Vd >12 l = 0,2 l/Kg) o al interior de las células (Vd > 40 l = 0,6 l/Kg), mientras que Vd bajos (< 3 l = 0,04 l/Kg) indican que el fármaco está en el plasma sanguíneo y, por tanto, tiene más oportunidad de pasar a leche.
3. Persistir en leche de la madre en concentración significativa.
Depende del:
- Pico o Tiempo máximo: Tiempo necesario para alcanzar la concentración plasmática máxima desde la administración del fármaco. Es el momento, diferente para cada fármaco, en el que hay mayor posibilidad de excreción en leche materna. Evitando amamantar en ese momento, se minimiza dicha excreción.
- T1/2 o semivida de eliminación o tiempo medio de eliminación. Es el tiempo que tarda la concentración plasmática de una sustancia en reducirse a la mitad, generalmente a través de su eliminación renal. Los T1/2 son fijos y diferentes para cada sustancia y varían desde segundos a días. Son preferibles durante la lactancia los medicamentos de eliminación rápida. Se sabe que pasadas 3 semividas de eliminación se ha eliminado del organismo el 90% del medicamento, tras 5 semividas el 97% y tras 7 semividas apenas queda un 1% del fármaco en el organismo (Briggs 2012). Según los meses de lactancia y lo peligroso de una sustancia podemos minimizar su paso desde sangre a leche esperando a amamantar el tiempo necesario para que el organismo quede más o menos “lavado” de esa sustancia. En la mayoría de los fármacos no valdrá la pena, pero en fármacos muy agresivos, como los del tratamiento del cáncer, convendrá esperar de 5 a 7 vidas medias antes de volver a amamantar.
- Pasar a sangre del lactante: De nuevo la biodisponibilidad es un factor influyente. Cuando el lactante toma leche en la que hay una determinada cantidad del fármaco tomado por la madre, debe aún absorberlo en su intestino para que llegue a su circulación. Las sustancias de índole proteica como algunas hormonas, inmunoglobulinas o vacunas, y ciertos medicamentos que precisan recubrimiento entérico para absorberse, como el omeprazol, cuando llegan a la leche de la madre, carecen de él y son destruidos en el estómago del lactante. Los medicamentos con forma única de administración parenteral lo son por tener biodisponibilidad oral nula; es el caso de los aminoglucósidos, por ejemplo, que, como mucho provocaran disbacteriosis intestinal sin pasar a sangre del lactante. Ciertos antibacterianos como las tetraciclinas y las quinolonas llegan a la leche en cantidad pequeña y deja de ser significativa al quedarse con el calcio de la leche y no ser absorbidos por el lactante.
- Ser una sustancia toxica para el lactante. Los medicamentos con pocos y leves efectos secundarios, los de uso habitual en Pediatría y, mejor aún, en lactantes pequeños o Neonatología, no causaran problema por recibirlos a dosis subterapeúticas a través de la leche de la madre.
Así pues, para fármacos sin datos publicados de su excreción en leche, nos basaremos en estos datos de farmacocinética para valorar el riesgo de administrarlos a una madre lactante:
- Los fármacos con absorción plasmática nula o insignificante, y los que se supone que no pasaran de plasma a leche por elevado peso molecular o alto porcentaje de unión a proteínas pueden ser valorados como compatibles o de bajo riesgo. Por todo lo anteriormente expuesto, fármacos que se consideran de aplicación tópica o local en piel, oído externo, bronquios o intestino, como cremas, lociones, gotas óticas, antiácidos y medicación inhalada para el asma y la rinitis no deberían preocuparnos de que los tome una madre lactante.
- Un peso molecular mayor de 1.000 Dalton.
- Un porcentaje de unión a proteínas >90% son garantías teóricas de un paso a leche no significativo.
Hay ciertos fármacos que se consideran de más riesgo e incluso algunos contraindicados durante la lactancia como aparecen reflejados en las siguientes tablas.
Los antineoplásicos, drogas de abuso, litio, salicilatos, antihistamínicos de 1a generación que causan sedación, la codeína por si la madre es metabolizadora rápida de codeína a morfina, el nitroprusiato que se metaboliza en cianuro, la pirimetamina que inhibe el ácido fólico, y todos aquellos que pueden dar efectos secundarios graves o de los que se dispone de poca información o son demasiado recientes y con poca experiencia de uso, en especial los que tengan pesos moleculares muy bajos (inferior a 500 Dalton), estén unidos a proteínas plasmáticas en proporción inferior al 85%, sean muy liposolubles o con una biodisponibilidad elevada (mayor del 70%) y un T1/2 superior a 12 horas.
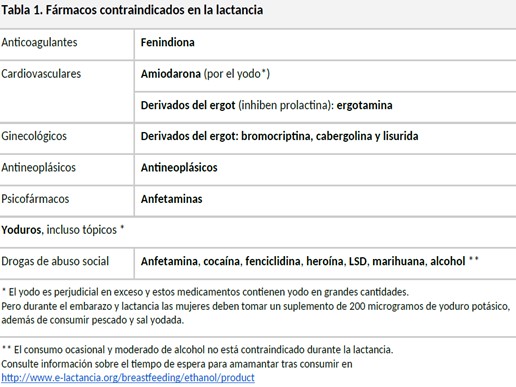
Fuente: https://apilam.org. http://www.e-lactancia.org.

Fuente: https://apilam.org. http://www.e-lactancia.org.
Algunos medicamentos pueden disminuir la producción láctea por inhibición de la prolactina: alcaloides del Ergot, estrógenos, anticolinérgicos (antiespasmódicos o antihistamínicos de 1a generación), el uso prolongado de diuréticos, especialmente tiazídicos, el abuso de pseudoefedrina, gonadotropinas, antiparkinsonianos precursores de la dopamina y prostaglandinas en la primera semana posparto.
Fármacos con datos publicados de su excreción en leche.
Apenas de una tercera parte de medicamentos comercializados se ha llegado a medir y publicar que cantidad de medicamento pasa a la leche. Estas publicaciones pueden dar información de los efectos del fármaco en el lactante o en la lactancia, de su concentración en leche materna y de la dosis que recibe el lactante a través de dicha leche, pudiendo calcularse la dosis relativa (DR) o porcentaje respecto a la dosis terapéutica habitual, sea en relación con la dosis de la madre (ponderada por kg de
peso) o en relación con la dosis terapéutica pediátrica.
- Dosis teórica del lactante: es la cantidad máxima en mg/kg/día que puede recibir un lactante de la medicación que toma su madre, estimándola a partir de concentraciones publicadas de medicamentos en leche materna y asumiendo una ingestión diaria de 150 ml de leche por kilogramo de peso corporal. Multiplicando los miligramos de una sustancia que hay en cada mililitro de leche materna por 150, obtendremos la dosis en mg/kg/día que recibe el lactante:
Dosis teórica (mg/kg/día) = Concentración en leche materna (mg/ml) x 150
- Dosis relativa del lactante (DR): es la relación porcentual entre la dosis materna de un medicamento y la dosis teórica que le llega al lactante a través de la leche, expresadas ambas en mg por kilo de peso al día. Estimamos un peso medio materno de 60 Kg cuando la dosis de adulto no esté expresada en mg/kg/día:
Dosis relativa (%) = Dosis teórica del lactante (mg/k/día) x 100
Dosis de la madre (mg/k/día)
- Porcentaje de la dosis terapéutica. Sugiero este índice, similar al anterior pero aplicable a los medicamentos de uso pediátrico: es la relación porcentual entre la dosis teórica máxima que recibiría el lactante a través de la leche materna y la dosis usual de tratamiento pediátrico:
% dosis terapéutica = Dosis teórica del lactante (mg/k/día) x 100
Dosis pediátrica habitual (mg/k/día)
Se consideran seguras cifras inferiores al 10% en cualquiera de estos dos últimos porcentajes para la mayoría de los medicamentos, que no sean antineoplásicos. Una interpretación tranquilizadora para estos indicadores es traducirlos al número de días que hay que seguir mamando leche con medicamento para acabar tomando la dosis de un día que le correspondería al lactante: 10 días para un 10%, 50 días para un 2% o 1000 días para un 0,1%, por ejemplo.
Para una mejor comprensión de los cálculos de este apartado puede verse el siguiente caso práctico:
Queremos saber que dosis de ibuprofeno recibe un lactante cuya madre está tomando este medicamento por un dolor de muelas. Encontramos en una publicación que la concentración media de ibuprofeno en leche de mujeres que toman este medicamento es de 0,5 microgramos por mililitro de leche.
Así pues: Ibuprofeno en leche: 0,5 μg /ml. Para saber la dosis teórica que toma a través de la leche de su madre la dividiremos por 1.000 para convertir los μg en mg y la multiplicaremos por 150, que son los ml por kilogramo de peso de leche que un lactante pequeño toma de media cada día:
Dosis teórica: 0,5 / 1.000 x 150 = 0,075 mg/kg/día
Para saber cuánto es esto respecto a la dosis habitual de ibuprofeno en Pediatría (recordemos que se prescribe a 40 mg/kg/día) haremos una sencilla regla de tres para calcular el porcentaje: si 40 es el 100% de la dosis diaria, 0,075 será:
Dosis relativa: 0,075 x 100 / 40 = 0,2%
Es decir, una dosis relativa muy pequeña, insignificante, muy inferior al 10% (por debajo del 10% de la dosis habitual, la mayoría de los medicamentos se consideran seguros) que no va a producirle ningún problema al lactante ya que va a recibir menos de la centésima parte de la dosis que le correspondería tomar si tuviésemos que dárselo (0,2% es la quinta parte de la centésima parte!).
Dentro de la medicación de uso frecuente, encontramos compatibilidad en estos grupos de medicamentos:
- Analgésicos y Antiinflamatorios (no opioides)
El paracetamol o el ibuprofeno no causan ningún problema en la lactancia. En caso de cuadros gripales o catarrosos conviene evitar los medicamentos con varios principios activos como los antigripales y decantarse por medicamentos con un solo principio activo. Este grupo de medicamentos se suelen administrar de forma puntual (especialmente en el periodo posparto).
Un aspecto para tener en cuenta en relación con los analgésicos, concretamente a la aspirina del grupo de AINE (Antiinflamatorios No Esteroideos) es el siguiente: se relacionó el consumo de aspirina con la aparición de síndrome de Reye, especialmente en la primera infancia, por lo que, en muchos países se desaconsejó su uso en menores de 12-16 años (Unsworth 1987).
El síndrome de Reye es una enfermedad pediátrica grave que se caracteriza por una inflamación cerebral (encefalopatía) y hepática a causa de la ingesta de aspirina. Por esta razón, ya no es el analgésico de elección de uso pediátrico y ha sido sustituido por el paracetamol.
Aunque se han detectado niveles plasmáticos bajos en el lactante (Unsworth 1987), no se han descrito casos de Síndrome de Reye por aspirina a través de la leche materna y se considera muy improbable que pueda ocurrir con dosis aisladas. (Shepherd 2020).
El ácido acetilsalicílico se excreta en pequeña cantidad en leche materna (Datta 2017, Athavale 2013, Bailey 1982), siendo insignificante cuando las dosis maternas de aspirina son menores de 500 mg como en el tratamiento crónico como antiagregante, por ejemplo (Datta 2017).
Diversas sociedades médicas, expertos y consensos de expertos consideran seguro o probablemente seguro el uso aislado ocasional o a dosis antiagregante de aspirina durante la lactancia (Datta 2017, Rowe 2013, Sachs 2013, Bell 2011, Chen 2010, Bar-Oz 2003, OMS 2002, Spigset 2000).
Con dosis maternas en el rango terapéutico habitual analgésico-antipirético-antiinflamatorio hay tres publicaciones antiguas sobre efectos secundarios en el lactante: un caso muy dudoso de intoxicación salicílica en periodo neonatal (Clark 1981), una trombocitopenia en un lactante (Terragna 1967) y una crisis hemolítica en un neonato de 23 días afecto de deficiencia de glucosa-6 fosfato deshidrogenasa (Harley 1962).
Otros trabajos no han encontrado ningún problema en lactantes cuyas madres tomaban aspirina (Ito 1993).
Para su uso en dosis habituales como antiinflamatorio, analgésico o antipirético, son preferibles alternativas conocidas más seguras durante la lactancia (Davanzo 2014, Bloor 2013, Sachs 2013, Worthington 2013, Risser 2009, WHO 2002, Janssen 2000).
- Antibióticos
Si es necesario un antibiótico, casi todos los habituales como, por ejemplo, penicilinas, cefalosporinas, azitromicina o claritromicina son compatibles con la lactancia. Si es necesaria una quinolona, priorizar el norfloxacino o el ciprofloxacino (Chin 2001).
Con respecto al grupo de las sulfamidas, se deberían evitar durante el primer mes dado que podrían interferir en la unión de la bilirrubina a la albúmina. Este grupo de antibióticos se debe evitar cuando el lactante presenta déficit de Glucosa-6-fosfato deshidrogenasa dado que, al interferir en dicha unión bilirrubina-albúmina, pueden aumentar los niveles de bilirrubina libre en plasma (Hale 2017) por lo que conviene vigilar ictericia en el lactante. Ito (1993) reportó alimentación deficiente en algunos lactantes cuyas madres tomaron sulfametoxazol.
Con respecto a la tetraciclina, se excreta en leche materna en cantidad clínicamente no significativa y la absorción intestinal por parte del lactante está muy disminuida por formarse quelatos inabsorbibles con el calcio lácteo. De hecho, no se han observado problemas en lactantes cuyas madres la tomaban (Prakash 1990).
Los niveles en plasma de dichos lactantes fueron indetectables o muy bajos (Posner 1954, Graf 1959). No obstante, con un tratamiento prolongado, como en el tratamiento del acné, podría haber riesgo de afectación del cartílago de crecimiento, la coloración de dientes o la flora intestinal del lactante, por lo que es mejor una alternativa más segura durante la lactancia (Hale 2017).
Conviene tener en cuenta la posible falsa negatividad de cultivos en lactantes febriles cuyas madres toman antibióticos, así como la posibilidad de gastroenteritis por alteración de la flora intestinal (Arbex 2010, Ito 1993).
La AAP (Academia Americana de Pediatría) la considera medicación usualmente compatible con la lactancia.
Los aminoglucósidos como la neomicina, kanamicina o gentamicina se administran habitualmente vía parenteral como tratamiento antibiótico posparto. A pesar de que se pueden excretar a la leche materna, su baja disponibilidad oral (por esa razón se administran vía parenteral) hace altamente improbable que se absorban a nivel intestinal del bebé salvo en prematuros y periodo neonatal inmediato en los que puede haber mayor permeabilidad intestinal. (Briggs 2017, Chin 2001).
Como en el caso de las sulfamidas, conviene tener en cuenta la posible falsa negatividad de cultivos en lactantes febriles cuyas madres toman antibióticos, así como la posibilidad de gastroenteritis por alteración de la flora intestinal (Arbex 2010, Ito 1993).
En relación con las Cefalosporinas de tercera generación (ceftriaxona, cefotaxima), aunque se consideran seguras durante la lactancia (baja absorción oral), pueden alterar la flora intestinal del bebé (Ilett 2006,Ito 1993). Para contrarrestar esta alteración, la lactancia materna aporta lactobacillus que recolonizan rápidamente el intestino del bebé.
Las cefalosporinas se administran en neonatos y se debe tener en cuenta que la vida media de las cefalosporinas es 3 a 4 veces mayor en plasma de neonatos con respecto al plasma materno.
Tal y como indica la bibliografía sobre la mayoría de las cefalosporinas de las que se tienen datos, no se excretan en leche materna en cantidad clínicamente significativa y no se han observado problemas en lactantes cuyas madres fueron tratadas con este grupo de antibióticos. En el caso de la cefalexina que es una cefalosporina de primera generación y es uno de los antibióticos indicados en caso de mastitis se ha publicado un caso de reacción alérgica a través de la leche materna en un lactante previamente sensibilizado tras la administración de otra cefalosporina por vía intravenosa (Chiu 2019).
En el caso de la cefalexina, es una cefalosporina de primera generación y es uno de los antibióticos indicados en caso de mastitis (ABM protocolo nº 4, Jahanfar 2013).
Se ha publicado un caso de reacción alérgica a cefalexina a través de la leche materna en un lactante previamente sensibilizado tras la administración de otra cefalosporina por vía intravenosa (Chiu 2019).
Las cefalosporinas son muy utilizadas en Pediatría con muy buena tolerancia, incluso desde el periodo neonatal, por lo que es muy improbable que, en pequeñas cantidades a través de la leche, puedan causar problemas al lactante.
- Antibióticos y mastitis
Los tratamientos antibióticos de primera línea en mastitis (ABM 2022 protocolo nº 36), son compatibles con la lactancia.
Primera línea:
Se recomiendan como opciones principales dicloxacilina o flucloxacilina 500 mg, 4 veces al día, durante 10–14 días. Si no están disponibles, puede usarse cloxacilina, aunque su absorción oral es más variable. También se incluye cefalexina 500 mg, 4 veces al día, durante 10–14 días, destacando que ofrece una cobertura más amplia, incluyendo algunos bacilos gramnegativos, y que no necesita separarse de las comidas.
Segunda línea:
Se proponen clindamicina300 mg, 4 veces al día, durante 10–14 días, o trimetoprim-sulfametoxazol a dosis de doble concentración, 2 veces al día, también durante 10–14 días.
Precauciones importantes:
El trimetoprim-sulfametoxazol no se recomienda en madres de niños con déficit deG6PD. Además, debe usarse con precaución si el lactante es prematuro o presenta hiperbilirrubinemia, especialmente si tiene menos de 30 días de vida.
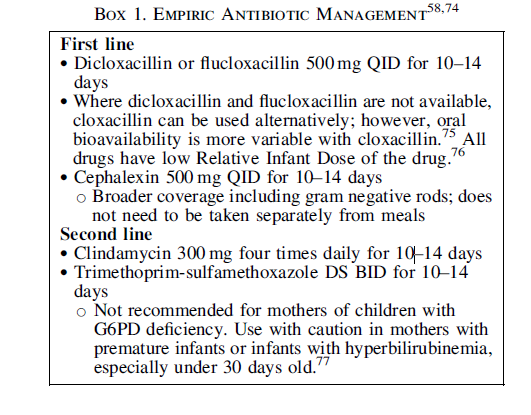
Tabla extraída de protocolo nº 36 de American Breastfeeding Medicine, ABM (Mitchell 2022)
- Inhaladores para el tratamiento del asma
Los broncodilatadores inhalados se consideran compatibles con la lactancia. Aunque para varios fármacos de este grupo —como salbutamol/albuterol, salmeterol, formoterol, ipratropio o tiotropio— no siempre existen estudios directos en mujeres lactantes, las fuentes especializadas y las revisiones disponibles coinciden en que su paso a la leche materna se espera muy bajo, debido a su escasa absorción sistémica y a los bajos niveles plasmáticos maternos tras la administración por vía inhalatoria.
Por este motivo, cuando existe alternativa inhalada, esta suele ser preferible a la vía oral, ya que produce una menor exposición sistémica materna y, por tanto, previsiblemente un menor paso a la leche materna. En consecuencia, los broncodilatadores inhalados se consideran de bajo riesgo durante la lactancia y pueden utilizarse cuando estén clínicamente indicados (Hale 2017, Lactmed, Amir 2011, National Asthma 2004, Ellsworth 1994).
- Gotas óticas y oculares
En relación con las gotas de aplicación ótica u ocular, la absorción sistémica suele ser muy baja, por lo que el paso a la leche materna se considera, en general, mínimo o clínicamente poco relevante. Por ello, la mayoría de los preparados óticos y oftálmicos son compatibles con la lactancia, aunque siempre conviene valorar el principio activo concreto y la situación clínica.
En el caso de los preparados oculares que contienen ácido bórico o boratos, la absorción sistémica es muy bajaoinsignificante. Como medida adicional, para reducir todavía más la absorción, puede realizarse oclusión del conducto lagrimal presionando en el canto interno del ojo durante al menos 1 minuto tras la instilación y retirando el exceso de solución.
- Hormonas
Muchas terapias hormonales son compatibles con la lactancia. En particular, la insulina, la levotiroxina y los corticoides de uso habitual presentan, en general, un perfil compatible. La levotiroxina es además un componente normal de la leche humana, y el tratamiento adecuado del hipotiroidismo materno puede favorecer una lactancia normal. En el caso de los corticoides sistémicos, las cantidades que pasan a la leche suelen ser muy bajas; aun así, las dosis medias-altas pueden reducir de forma transitoria la producción de leche.
En el caso de la insulina, de hecho, es un componente que existe en la leche materna y disminuye el riesgo de diabetes mellitus en lactantes amamantados (Sadauskaite-Kuehne 2004).
La poca cantidad de insulina que se absorbe vía oral promueve la maduración del intestino, induce la tolerancia a la insulina y previene la diabetes tipo 1 (O´Reilly 2011, Maldova 2006).
Las necesidades de insulina en madres diabéticas que dan pecho disminuyen un 25% tras el parto, por lo que precisan un mayor autocontrol y hay mayor necesidad de incremento calórico (500 a 800 Kcal/día).
Se debe iniciar lactancia materna de forma precoz y frecuente, ya que la lactogénesis puede estar retrasada en madres diabéticas. (Matias 2014).
Las madres diabéticas que amamantan mejoran su control metabólico durante la lactancia. La American Diabetes Association recomienda alentar a las mujeres con diabetes a amamantan.
- Inmunosupresores
Con respecto a ciclosporina y tacrolimus, la evidencia disponible indica que la exposición del lactante a través de la leche materna suele ser baja. En el caso del tacrolimus, las concentraciones en leche son reducidas y las guías de expertos estadounidenses y europeas lo consideran aceptable durante la lactancia; en lactantes amamantados de forma exclusiva puede valorarse monitorización clínica y, si existe sospecha de toxicidad, determinación de niveles séricos. Con ciclosporina, numerosos expertos y guías profesionales también la consideran de bajo riesgo y compatible con la lactancia, aunque igualmente se recomienda vigilancia clínica del lactante y valorar la determinación de niveles séricos si fuera necesario.
En el caso de los anticuerpos monoclonales, como natalizumab o golimumab, su gran tamaño molecular y naturaleza proteica hacen prever una absorción oral muy baja por parte del lactante. Natalizumab se excreta en cantidades bajas pero medibles en la leche; en la información disponible no se ha detectado en el suero de los lactantes estudiados y la mayoría de las guías expertas consideran aceptable la lactancia durante su uso. No obstante, conviene señalar que algunas fichas técnicas siguen siendo más conservadoras y recomiendan suspender la lactancia durante el tratamiento. Por su parte, golimumab es casi indetectable en la leche materna, su absorción intestinal por,el lactante se considera mínima y, en los datos publicados, no se han observado diferencias en crecimiento, desarrollo o infecciones respecto a lactantes no expuestos. Kuczaj 2024, Akamine 2021, Ciplea 2020, Hiramatsu 2018, Kociszewska 2018,Mazzuoccolo 2014,).
En conjunto, la evidencia disponible no ha mostrado efectos adversos relevantes en la mayoría de los lactantes expuestos a estos fármacos a través de la leche materna, aunque la decisión debe individualizarse según el medicamento, la edad del lactante, la dosis materna y la necesidad clínica del tratamiento
- Ansiolíticos y antidepresivos
En relación con los ansiolíticos, el uso ocasionaly a ladosis mínima eficazde benzodiacepinas puede ser compatible con la lactancia (Kelly 2012, Rubin 2004, Iqbal 2002, Hägg 2000). Entre ellas, lorazepamy oxazepamson las opciones preferidas por su vida media relativamente corta (Rowe 2013), y sus niveles bajos en leche; midazolam también puede emplearse con cautela cuando se utiliza de forma puntual. Debe evitarse, siempre que sea posible, el uso crónico de benzodiacepinas de vida media larga, sobre todo enrecién nacidos, prematuros o cuando la madre recibe otros fármacos sedantes, por el mayor riesgo de acumulación (Sachs 2013). Se recomienda vigilar en el lactante somnolencia, depresión respiratoria, dificultad para alimentarseyganancia ponderal adecuada. Además, NICE aconsejano compartir camacon el bebé cuando se han utilizado medicamentos sedantes, por el aumento del riesgo de eventos graves relacionados con el sueño (UNICEF 2018, 2017, 2014 y 2013, Landa 2012, ABM 2008, UNICEF 2006).
Con respecto a los antidepresivos, la formulación actual más prudente es que el tratamiento no debe retrasarse cuando la depresión materna es clínicamente significativa, ya que la depresión no tratada también tiene consecuencias para la díada madre-hijo. Si no existe antecedente de buena respuesta previa a otro fármaco, la sertralina suele considerarse una de las primeras opciones durante la lactancia por sus concentraciones bajas en leche, niveles plasmáticos infantiles generalmente indetectables o muy bajos y ausencia de efectos adversos relevantes en la mayoría de los seguimientos publicados; junto con paroxetina, es uno de los Inhibidores Selectivos de la Recaptación de Serotonina (ISRS) preferidos en guías actuales (Schoretsanitis 2019, Pogliani 2019, Weisskopf 2017, Salazar 2016).
Puede haber problemas transitorios durante el periodo neonatal inmediato, como el síndrome de discontinuación de antidepresivos o una hiperestimulación de serotonina, en recién nacidos a término o prematuros que nacen con niveles plasmáticos altos porque sus madres toman sertralina durante el embarazo (Müller 2013, Hale 2010). Además, las madres tratadas con ISRS durante el embarazo y el posparto pueden presentar más dificultades con el inicio y mantenimiento de la lactancia, por lo que a menudo precisan apoyo adicional.
Aunque con menos frecuencia que otros antidepresivos, la sertralina puede causar galactorrea (Nebhinani 2013), con o sin hiperprolactinemia (Petit 2003, Trenque 2011). Puede darse también disminución transitoria de la producción de leche que mejora con una buena hidratación (Holland 2000).
Dentro de los antidepresivos tricíclicos, las guías actuales suelen considerar de elección a nortriptilinaeimipramina; laamitriptilina también puede utilizarse cuando está clínicamente indicada y, en general, produce niveles bajos en leche y pocos efectos adversos descritos en lactantes (Breyer 1995, Yoshida 1999, Wisner 1996, Brixen 1982), especialmente si son mayores de 2 meses.
Las mujeres enfermas de depresión durante el embarazo necesitan más apoyo a la lactancia por tener más riesgo de problemas y cese precoz de la lactancia (Grzeskowiak 2018, Leggett 2017).
El protocolo nº 18 de la ABM, hace las siguientes consideraciones en relación con los tratamientos antidepresivos durante la lactancia:
- Elegir aquella medicación psicotrópica que tenga evidencia en mujeres lactantes. Para ello, medicación más antigua que tenga datos publicados relativos a su compatibilidad con la lactancia materna es preferible a antidepresivos de reciente comercialización con información limitada.
- Aunque monitorizar la concentración de un antidepresivo en plasma del bebé es complicado como rutina en la práctica clínica, es la medida más efectiva para evaluar la exposición de un bebé lactante a determinada medicación.
- Los factores claves para determinar la excreción de un antidepresivo a la leche materna son los siguientes: las características farmacocinéticas del medicamento antidepresivo (biodisponibilidad oral, t1/2, tmax, pKa, volumen de distribución, peso molecular,liposolubilidad del fármaco, fijación a proteínas plasmáticas) y la cantidad de fármaco que recibe el lactante a través de la leche materna: cantidad leche, calostro o leche madura, concentración de medicación en leche, vaciado del pecho en la toma anterior y la capacidad del bebé lactante en absorber, metabolizar y excretar la medicación.
- Datos publicados en este metaanálisis de Weissman y col. En 2004, revelaron que todos los antidepresivos se detectaban en leche materna en mayor y menor grado, pero no todos se detectaron en plasma del lactante.
- Los niveles en plasma del lactante de nortriptilina, paroxetina y sertralina fueron indetectables en la mayoría de los casos. Los niveles de citalopram y fluoxetina se excedían en el DR del 10% de la madre siendo 17% y 22% respectivamente.
- Se han reportado escasos efectos adversos de antidepresivos.
- Vacunas
Salvo excepciones muy concretas, las vacunas son compatibles con la lactancia. Las recomendaciones actuales indican que ni las vacunas inactivadas ni la mayoría de las vacunas de virus vivos administradas a una mujer lactante afectan a la seguridad de la lactancia para la madre o el lactante. Conviene destacar sobre todo dos situaciones especiales: la vacuna antivariólica (vaccinia/smallpox), contraindicada durante la lactancia por el riesgo teórico de transmisión por contacto al lactante, y la vacuna frente a la fiebre amarilla, que debe evitarse si es posible en mujeres lactantes, especialmente cuando amamantan a lactantes pequeños, ya que se han descrito casos de enfermedad neurológica asociada a transmisión del virus vacunal a través de la leche. Cuando el viaje a una zona endémica no puede posponerse, la indicación de la vacuna frente a la fiebre amarilla debe individualizarse valorando riesgos y beneficios.
En relación con la vacunación frente a la COVID-19, en la actualidad, ni la OMS ni los CDC recomiendan suspender o retrasar la lactancia tras la vacunación. La OMS señala que vacunarse durante la lactancia es importante para proteger a la madre y a su familia y que no se han identificado problemas de seguridad para las mujeres que amamantan ni para sus bebés. Los CDC indican que, en 2025–2026, la recomendación para mujeres lactantes se basa en una toma de decisiones individualizada, con mayor beneficio esperado en quienes presentan mayor riesgo de enfermedad grave o son recientemente posparto.
La evidencia acumulada muestra que los efectos adversos maternos tras la vacunación frente a la COVID-19 son similares a los observados en la población general y que no se han descrito reacciones graves atribuibles a la vacunación en los lactantes amamantados. Además, tras la vacunación, especialmente con vacunas de ARNm, se detectan anticuerpos anti-SARS-CoV-2 en la leche materna, lo que podría contribuir a la protección del lactante. Los datos de LactMed también indican que se detecta poca o ninguna cantidad de ARNm vacunal en la leche. En una minoría de mujeres se han descrito cambios transitorios en la producción o en el color de la leche, generalmente autolimitados y con recuperación en pocos días, por lo que estos hallazgos no justifican interrumpir la lactancia.
Tras la vacunación frente a la COVID-19 puede aparecer adenopatía axilar ipsilateral, palpable o detectada en pruebas de imagen. Se trata de un efecto adverso conocido y habitualmente benigno. Las guías EUSOBI de 2023 recomiendan no retrasar las pruebas de imagen mamaria por este motivo y, en pacientes sin antecedentes de cáncer de mama ni hallazgos sospechosos, consideran benigna la adenopatía unilateral reciente tras la vacunación, evitando estudios innecesarios (Schiaffino 2023).
- Inmunoterapia
La inmunoterapia con alérgenos se considera compatible con la lactancia. Los consensos de expertos no han identificado un aumento del riesgo por prescribir o mantener este tratamiento en mujeres lactantes ni un riesgo conocido para el lactante amamantado. Por ello, la lactancia no constituye una contraindicación para la inmunoterapia alergénica, incluida la inmunoterapia con venenos cuando está clínicamente indicada.
Dónde Consultar
Aunque algunos laboratorios farmacéuticos están haciendo un esfuerzo para informar verazmente sobre lactancia en sus fichas técnicas, aun no es la tónica habitual. Normalmente ni el prospecto ni la ficha técnica ni el Vademécum nos van a ser de utilidad.
Podemos obtener información rigurosa y fidedigna de varias maneras:
- En la página web PubMed de la US National Library of Medicine https://pubmed.ncbi.nlm.nih.gov" target="_blank">https://pubmed.ncbi.nlm.nih.gov con la estrategia de búsqueda (breastfeeding or breast feeding or breast milk or colostrum or lactation or prolactin) and fármaco, siendo fármaco el nombre en inglés del fármaco a investigar. Obtendremos los resúmenes y eventualmente el texto completo de las publicaciones que hay acerca de ese medicamento en relación con la lactancia materna.
- En la página web Drugs and Lactation Database (LactMed) de la US National Library of Medicine https://www.ncbi.nlm.nih.gov/books/NBK501922/" target="_blank">https://www.ncbi.nlm.nih.gov/books/NBK501922/ Haciendo directamente una búsqueda del medicamento en ingles obtenemos las referencias bibliográficas y el comentario razonado de los datos más relevantes de las mismas (niveles en leche materna, niveles en plasma u orina del lactante y efectos en el lactante y en la lactancia).
- En la página web de Compatibilidad de fármacos con la lactancia http://www.elactancia.org" target="_blank">http://www.elactancia.org de la Asociación para la Promoción e Investigación en Lactancia Materna (APILAM) http://apilam.org." target="_blank">http://apilam.org. En esta página, basada en trabajos publicados, obtenemos directamente una ficha con la clasificación de riesgo del fármaco consultado junto con un comentario-resumen de la bibliografía al respecto, el grupo terapéutico del fármaco, sus marcas más habituales, una alternativa más segura posible, los datos farmacocinéticos disponibles (peso molecular, porcentaje de fijación a proteínas plasmáticas, índice leche/plasma, volumen de distribución, tiempo máximo, semivida de eliminación, dosis teórica recibida y dosis relativa respecto a la madre o habitual pediátrica) y el listado de referencias bibliográficas con acceso al abstract o texto completo. Se trata de una página en español y con versión inglesa, que permite una consulta rápida con posibilidad de profundizar valorando la farmacocinética y leyendo la bibliografía. Es de uso gratuito, de sencillo manejo y compatible con todos los sistemas operativos de ordenadores, tabletas y teléfonos móviles. Ha tenido una buena acogida por la Academy of Breastfeeding Medicine (ABM, protocolo 15), es utilizada anualmente por más de seis millones de usuarios que realizan unos diez millones de consultas y está avalada por la IHAN España entre otros organismos sanitarios. Si tras consultar esta página persisten las dudas, se puede remitir una consulta al correo electrónico elactancia.org@gmail.com.
BIBLIOGRAFÍA
- Academy of Breastfeeding Medicine Protocol Committee. (2008). ABM clinical protocol #6: guideline in co-sleeping and breastfeeding. Revision, March 2008. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 3(1), 38–43.
- Backstrand, J. R., Goodman, A. H., Allen, L. H., & Pelto, G. H. (2004). Pulque intake during pregnancy and lactation in rural Mexico: alcohol and child growth from 1 to 57 months. European Journal of Clinical Nutrition, 58(12), 1626–1634.
- Baheiraei, A., Shamsi, A., Khaghani, S., Shams, S., Chamari, M., Boushehri, H., & Khedri, A. (2014). The effects of maternal passive smoking on maternal milk lipid. Acta Medica Iranica, 52(4), 280–285.
- Ball H, Blair P. Health professionals’ guide to: Caring for your baby at night. UNICEF UK Baby Friendly Initiative; 2021.
- Blair PS, Ball HL, McKenna JJ, et al. Bedsharing and breastfeeding: The Academy of Breastfeeding Medicine Protocol #6, revision 2019. Breastfeed Med. 2020;15(1):5-16.
- Centers for Disease Control and Prevention. Tobacco and electronic cigarettes [Internet]. Atlanta: CDC; 2025 Sep 23.
- Centers for Disease Control and Prevention. Health problems caused by second hand smoke [Internet]. Atlanta: CDC; 2025 Jan 3.
- Chien, Y.-C., Huang, Y.-J., Hsu, C.-S., Chao, J. C.-J., & Liu, J.-F. (2009). Maternal lactation characteristics after consumption of an alcoholic soup during the postpartum “doing-the-month” ritual. Public Health Nutrition, 12(3), 382–388.
- Codoñer-Franch, P., Hernández-Aguilar, M. T., Navarro-Ruiz, A., López-Jaén, A. B., Borja-Herrero, C., & Valls-Bellés, V. (2013). Diet supplementation during early lactation with non-alcoholic beer increases the antioxidant properties of breastmilk and decreases the oxidative damage in breastfeeding mothers. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 8(2), 164–169.
- Coiro, V., Alboni, A., Gramellini, D., Cigarini, C., Bianconi, L., Pignatti, D., … Chiodera, P. (1992). Inhibition by ethanol of the oxytocin response to breast stimulation in normal women and the role of endogenous opioids. European journal of endocrinology, 126(3), 213–216.
- Haastrup, M. B., Pottegård, A., & Damkier, P. (2014). Alcohol and breastfeeding. Basic & Clinical Pharmacology & Toxicology, 114(2), 168–173.
- Harris M, Schiff DM, Saia K, et al. Academy of Breastfeeding Medicine Clinical Protocol #21: breastfeeding in the setting of substance use and substance use disorder, revised 2023. Breastfeed Med. 2023;18(10):715-733.
- Ho, E., Collantes, A., Kapur, B. M., Moretti, M., & Koren, G. (2001). Alcohol and breast feeding: Calculation of time to zero level in milk. Neonatology, 80(3), 219–222.
- Ilett, K. F., Hale, T. W., Page-Sharp, M., Kristensen, J. H., Kohan, R., & Hackett, L. P. (2003). Use of nicotine patches in breast-feeding mothers: transfer of nicotine and cotinine into human milk. Clinical Pharmacology and Therapeutics, 74(6), 516–524.
- Jones W. Smoking, smoking cessation and breastfeeding [Internet]. The Breastfeeding Network; amended 2025 Jan [cited 2026 Apr 11]
- Koletzko, B., & Lehner, 1frauke. (2005). Beer and Breastfeeding. En Advances in Experimental Medicine and Biology (pp. 23–28). Boston: Kluwer Academic Publishers.
- Koren, G. (2002). Drinking alcohol while breastfeeding. Will it harm my baby? Canadian Family Physician Medecin de Famille Canadien, 48, 39–41.
- Landa Rivera, L., Díaz-Gómez, M., Gómez Papi, A., & Paricio Talayero, J. M. (2012). El colecho favorece la práctica de la lactancia materna y no aumenta el riesgo de muerte súbita del lactante. Dormir con los padres. Recuperado el 2 de agosto de 2021, de Pap.es website: https://pap.es/files/1116-1449-pdf/pap53_10.pdf" target="_blank">https://pap.es/files/1116-1449-pdf/pap53_10.pdf" target="_blank">https://pap.es/files/1116-1449-pdf/pap53_10.pdf
- Little, R. E., Anderson, K. W., Ervin, C. H., Worthington-Roberts, B., & Clarren, S. K. (1989). Maternal alcohol use during breast-feeding and infant mental and motor development at one year. The New England Journal of Medicine, 321(7), 425–430.
- Meek JY, Noble L; Section on Breastfeeding. Policy statement: Breastfeeding and the use of human milk. Pediatrics. 2022;150(1):e2022057988.
- Mennella, J. A. (2001). Regulation of milk intake after exposure to alcohol in mothers’ milk. Alcoholism, Clinical and Experimental Research, 25(4), 590–593.
- Mennella, Julie A., Pepino, M. Y., & Teff, K. L. (2005). Acute alcohol consumption disrupts the hormonal milieu of lactating women. The Journal of Clinical Endocrinology and Metabolism, 90(4), 1979–1985.
- Mgongo, M., Mosha, M. V., Uriyo, J. G., Msuya, S. E., & Stray-Pedersen, B. (2013). Prevalence and predictors of exclusive breastfeeding among women in Kilimanjaro region, Northern Tanzania: a population based cross-sectional study. International Breastfeeding Journal, 8(1), 12.
- Moon RY, Carlin RF, Hand I; Task Force on Sudden Infant Death Syndrome and Committee on Fetus and Newborn. Sleep-related infant deaths: updated 2022 recommendations for reducing infant deaths in the sleep environment. Pediatrics. 2022;150(1): e2022057990.
- Moretti, M. E., Lee, A., & Ito, S. (2000). Which drugs are contraindicated during breastfeeding? Practice guidelines. Canadian Family Physician Medecin de Famille Canadien, 46, 1753–1757.
- NHS. Breastfeeding and smoking [Internet]. [cited 2026 Apr 11]
- Reece-Stremtan, S., & Marinelli, K. A. (2022). ABM clinical protocol #21: Guidelines for breastfeeding and substance use or substance use disorder, revised 2015. En Breastfeeding (pp. 942–949). Elsevier.
- Rocha, B. de O., Machado, M. P., Bastos, L. L., Barbosa Silva, L., Santos, A. P., Santos, L. C., & Ferrarez Bouzada, M. C. (2020). Risk factors for delayed onset of lactogenesis II among primiparous mothers from a Brazilian Baby-Friendly Hospital. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 36(1), 146–156.
- Sachs, H. C., & Committee on Drugs. (2013). The transfer of drugs and therapeutics into human breast milk: an update on selected topics. Pediatrics, 132(3), e796-809.
- Schneider, C., Thierauf, A., Kempf, J., & Auwärter, V. (2013). Ethanol concentration in breastmilk after the consumption of non-alcoholic beer. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 8(3), 291–293.
- Szlagatys-Sidorkiewicz A, Zagierski M, Jankowska A, Łuczak G, Macur K, Bączek T, et al. Maternal smoking modulates fatty acid profile of breast milk. Acta Paediatr. 2013;102(9):e353-e359.
- Anderson PO. Drugs of abuse during breastfeeding. Breastfeed Med. 2018;13(6):405-407.
- Astley, S. J., & Little, R. E. (1990). Maternal marijuana uses during lactation and infant development at one year. Neurotoxicology and Teratology, 12(2), 161–168.
- Bartu A, Dusci LJ, Ilett KF. Transfer of methylamphetamine and amphetamine into breast milk following recreational use of methylamphetamine. Br J Clin Pharmacol. 2009;67(4):455-459.
- Bawa Z, Lewis D, Gavin PD, Libinaki R, Joubran L, El-Tamimy M, et al. An open-label feasibility trial of transdermal cannabidiol for hand osteoarthritis. Sci Rep. 2024;14(1):11792. doi:10.1038/s41598-024-62428-x.
- Briggs, G. G., Freeman, R. K., Towers, C. V., & Forinash, A. B. (s/f). Drugs in Pregnancy and Lactation: A Reference Guide to Fetal and Neonatal Risk.
- Centers for Disease Control and Prevention. Marijuana. In: Breastfeeding special circumstances [Internet]. Atlanta: CDC; 2024
- Centers for Disease Control and Prevention. Cannabis and Mental Health [Internet]. Atlanta: CDC; 2024
- Centers for Disease Control and Prevention. About CBD [Internet]. Atlanta: CDC; 2024.
- Centers for Disease Control and Prevention. Contraindications to Breastfeeding or Feeding Expressed Breast Milk to Infants [Internet]. 2025.
- Chomchai C, Chomchai S, Kitsommart R. Transfer of methamphetamine (MA) into breast milk and urine of postpartum women who smoked MA tablets during pregnancy: Implications for initiation of breastfeeding. J Hum Lact. 2016;32(2):333-339.
- Commission Regulation (EU) 2023/915 of 25 April 2023 on maximum levels for certain contaminants in food and repealing Regulation (EC) No 1881/2006. Off J Eur Union. 2023;L119:103-157.
- Cressman, A. M., Koren, G., Pupco, A., Kim, E., Ito, S., & Bozzo, P. (2012). Maternal cocaine uses during breastfeeding. Canadian Family Physician Medecin de Famille Canadien, 58(11), 1218–1219.
- DeLeo, V., Cella, S. G., Camanni, F., Genazzani, A. R., & Müller, E. E. (1983). Prolactin lowering effect of amphetamine in normoprolactinemic subjects and in physiological and pathological hyperprolactinemia. Hormone and Metabolic Research, 15(9), 439–443.
- European Commission. Hemp [Internet]. Brussels: Directorate-General for Agriculture and Rural Development
- Food and Drug Administration. 5 things to know about Delta-8 tetrahydrocannabinol—Delta-8 THC [Internet]. Silver Spring (MD): FDA; 2022.
- Fríguls B, Joya X, García-Algar O, Pallás CR, Vall O, Pichini S. A comprehensive review of assay methods to determine drugs in breast milk and the safety of breastfeeding when taking drugs. Anal Bioanal Chem. 2010;397(3):1157-1179
- Hale, T. W., & Pharmd Rowe, H. E. (2024). Medications and mothers’ milk 2017 (17a ed.). Nueva York, NY, Estados Unidos de América: Springer.
- Heidemann, S. M., & Goetting, M. G. (1990). Passive inhalation of cocaine by infants. Henry Ford Hospital Medical Journal, 38(4), 252–254.
- Oei, J. L. , Jaques, S. C., Kingsbury, A., Henshcke, P., Chomchai, C., Clews, S., Falconer, J., … 2014). Cannabis, the pregnant woman and her child: weeding out the myths. Journal of Perinatology: Official Journal of the California Perinatal Association, 34(6), 417–424.
- Ko, J. Y., Tong, V. T., Bombard, J. M., Hayes, D. K., Davy, J., & Perham-Hester, K. A. (2018). Marijuana use during and after pregnancy and association of prenatal use on birth outcomes: A population-based study. Drug and Alcohol Dependence, 187, 72–78.
- Lamvu G, Feranec J, Blanton E. Perioperative pain management: an update for obstetrician-gynecologists. Am J Obstet Gynecol. 2018 Feb;218(2):193-199.
- Lawrence, R. A., & Breastfeeding, L. R. M. (s/f). A guide for the medical profession (Eighth). Eighth.
- Machado AS, Bragança M, Vieira-Coelho M. Epigenetic effects of cannabis: A systematic scoping review of behavioral and emotional symptoms associated with cannabis use and exocannabinoid exposure. Drug Alcohol Depend. 2024;263:111401. doi:10.1016/j.drugalcdep.2024.111401.
- Moss MJ, Bushlin I, Kazmierczak S, Koop D, Hendrickson RG, Zuckerman KE, Grigsby TM.Cannabis use and measurement of cannabinoids in plasma and breast milk of breastfeeding mothers. Pediatr Res. 2021;90(4):861-8
- MotherToBaby. MDMA (Molly, Ecstasy). In: NCBI Bookshelf [Internet]. Brentwood (TN): Organization of Teratology Information Specialists; 2022
- National Library of Medicine (US). Cannabis. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development.
- National Library of Medicine (US). Cannabidiol. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development.
- National Library of Medicine (US). Cocaine. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development.
- National Library of Medicine (US). Methamphetamine. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development.
- National Library of Medicine (US). Heroin. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development.
- National Institute on Drug Abuse (NIDA). Cannabis (Marijuana) [Internet]. Bethesda (MD): NIDA; 2024.
- Petraglia, F., De Leo, V., Sardelli, S., Mazzullo, G., Gioffrè, W. R., Genazzani, A. R., & D’Antona, N. (1987). Prolactin changes after administration of agonist and antagonist dopaminergic drugs in puerperal women. Gynecologic and Obstetric Investigation, 23(2), 103–109.
- Reece-Stremtan Sarah, Campos Matilde, Kokajko Lauren, and The Academy of Breastfeeding Medicine. Breastfeeding Medicine. ABM Clinical Protocol #15: Analgesia and Anesthesia for the Breastfeeding Mother, Revised 2017. Breastfeed Med. 2017 Nov;12(9):500-506.
- Rodrigues RJ, Marques JM, Köfalvi A. Cannabis, Endocannabinoids and Brain Development: From Embryogenesis to Adolescence. Cells. 2024;13(22):1875. doi:10.3390/cells1322187.
- Rowe, H., Baker, T., & Hale, T. W. (2013). Maternal medication, drug use, and breastfeeding. Pediatric Clinics of North America, 60(1), 275–294.
- Steiner, E., Villén, T., Hallberg, M., & Rane, A. (1984). Amphetamine secretion in breast milk. European Journal of Clinical Pharmacology, 27(1), 123–124.
- Thompson, R., DeJong, K., & Lo, J. (2019). Marijuana use in pregnancy: A review: A review. Obstetrical & Gynecological Survey, 74(7), 415–428.
- Uso de sustancias - LSD. (s/f). Medlineplus.gov website: https://medlineplus.gov/spanish/ency/patientinstructions/000795.htm" target="_blank">https://medlineplus.gov/spanish/ency/patientinstructions/000795.htm" target="_blank">https://medlineplus.gov/spanish/ency/patientinstructions/000795.htm" target="_blank">https://medlineplus.gov/spanish/ency/patientinstructions/000795.htm">https://medlineplus.gov/spanish/ency/patientinstructions/000795.htm
- Vallersnes, O. M., Dines, A. M., Wood, D. M., Yates, C., Heyerdahl, F., Hovda, K. E., Dargan, P. I. (2016). Psychosis associated with acute recreational drug toxicity: a European case series. BMC Psychiatry, 16, 293.
- Volkow, N. D., Baler, R. D., Compton, W. M., & Weiss, S. R. B. (2014). Adverse health effects of marijuana use. The New England Journal of Medicine, 370(23), 2219–2227.
- Warner, T. D., Roussos-Ross, D., & Behnke, M. (2014). It’s not your mother’s marijuana: effects on maternal-fetal health and the developing child. Clinics in Perinatology, 41(4), 877–894.
- Winecker, R. E., Goldberger, B. A., Tebbett, I. R., Behnke, M., Eyler, F. D., Karlix, J. L., Bertholf, R. L. (2001). Detection of cocaine and its metabolites in breast milk. Journal of Forensic Sciences, 46(5), 1221–1223.
- Wise, M. S., Arand, D. L., Auger, R. R., Brooks, S. N., Watson, N. F., & American Academy of Sleep Medicine. (2007). Treatment of narcolepsy and other hypersomnias of central origin. Sleep, 30(12), 1712–1727.
- Worthington I, Pringsheim T, Gawel MJ, Gladstone J, Cooper P, Dilli E, Aube M, Leroux E, Becker WJ; Canadian Headache Society Acute Migraine Treatment Guideline Development Group. Canadian Headache Society Guideline: acute drug therapy for migraine headache. Can J Neurol Sci. 2013 Sep;40(5 Suppl 3): S1-S80. Review
- Wymore EM, Palmer C, Wang GS, Metz TD, Bourne DWA, Sempio C, et al. Persistence of Δ-9-tetrahydrocannabinol in human breast milk. JAMA Pediatr. 2021;175(6):632-634. doi:10.1001/jamapediatrics.2020.6098.
- Yang M, Feng Y, Zhang YL, Smith CM, Hou YN, Wang H, et al. Herbal formula MaZiRenWan (Hemp Seed Pill) for constipation: a systematic review with meta-analysis. Phytomedicine. 2021;82:153459.
- Berens, P., Labbok, M., & Academy of Breastfeeding Medicine. (2015). ABM clinical protocol #13: Contraception during breastfeeding, revised 2015. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 10(1), 3–12.
- Betrabet, S. S., Shikary, Z. K., Toddywalla, V. S., Patel, D., Vaidya, P., & Saxena, B. N. (1986). ICMR Task Force Study on hormonal contraception. Biological activity of ethinyl estradiol present in the breast milk. Contraception, 34(2), 169–175.
- Betrabet, S. S., Shikary, Z. K., Toddywalla, V. S., Toddywalla, S. P., Patel, D., & Saxena, B. N. (1987). ICMR Task Force Study on hormonal contraception. Transfer of norethisterone (NET) and levonorgestrel (LNG) from a single tablet into the infant’s circulation through the mother’s milk. Contraception, 35(6), 517–522.
- Chen, B. A., Reeves, M. F., Creinin, M. D., & Schwarz, E. B. (2011). Postplacental or delayed levonorgestrel intrauterine device insertion and breast-feeding duration. Contraception, 84(5), 499–504.
- College of Sexual and Reproductive Healthcare.UK Medical Eligibility Criteria for Contraceptive Use (UKMEC 2025). London: CoSRH; 2025
- Criterios médicos de elegibilidad para el uso de anticonceptivos Quinta edición 2015. Who.int
- Cunha AC1, R., Jg, D., & Aa, C. (2001). Intrauterine device and maternal copper metabolism during lactation. Contraception, 63, 37–39.
- Curtis KM, Nguyen AT, Tepper NK, Zapata LB, Snyder EM, Hatfield-Timajchy K, et al. U.S. Selected Practice Recommendations for Contraceptive Use, 2024. MMWR Recomm Rep. 2024;73(No. RR-3):1-77. doi:10.15585/mmwr.rr7303a1
- Faculty of Sexual & Reproductive Healthcare. FSRH statement: Ulipristal acetate and breastfeeding [Internet]. London
- Gainer, E., Massai, R., Lillo, S., Reyes, V., Forcelledo, M. L., Caviedes, R., … Bouyer, J. (2007). Levonorgestrel pharmacokinetics in plasma and milk of lactating women who take 1.5 mg for emergency contraception. Human Reproduction (Oxford, England), 22(6), 1578–1584.
- Goulding, A. N., Wouk, K., & Stuebe, A. M. (2018). Contraception and breastfeeding at 4 months postpartum among women intending to breastfeed. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 13(1), 75–80.
- Hatcher, R. A., Trussell, J., & Stewart, F. (s/f). Contraceptive Technology (17th ed.). Contraceptive Technology Communications.
- Jatlaoui, T. C., Riley, H., & Curtis, K. M. (2016). Safety data for levonorgestrel, ulipristal acetate and Yuzpe regimens for emergency contraception. Contraception, 93(2), 93–112.
- Madhavapeddi, R., & Ramachandran, P. (1985). Side effects of oral contraceptive use in lactating women--enlargement of breast in a breast-fed child. Contraception, 32(5), 437–443.
- Mandel, H., & Berant, M. (1985). Oral contraceptives and breastfeeding: haematological effects on the infant. Archives of Disease in Childhood, 60(10), 971–972.
- National Library of Medicine. Ulipristal. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Library of Medicine; 2026
- Nilsson, S., Mellbin, T., Hofvander, Y., Sundelin, C., Valentin, J., & Nygren, K. G. (1986). Long-term follow-up of children breast-fed by mothers using oral contraceptives. Contraception, 34(5), 443–457.
- Nilsson, S., Nygren, K. G., & Johansson, E. D. (1977). D-Norgestrel concentrations in maternal plasma, milk, and child plasma during administration of oral contraceptives to nursing women. American Journal of Obstetrics and Gynecology, 129(2), 178–184.
- Nilsson, Staffan, Nygren, K.-G., & Johansson, E. D. B. (1978). Transfer of estradiol to human milk. American Journal of Obstetrics and Gynecology, 132(6), 653–657.
- Nguyen, A. T., Curtis, K. M., Tepper, N. K., Kortsmit, K., Brittain, A. W., Snyder, E. M., Cohen, M. A., Zapata, L. B., & Whiteman, M. K. (2024). U.S. Medical Eligibility Criteria for Contraceptive Use, 2024. MMWR Recommendations and Reports, 73(4), 1–126.
- World Health Organization. Medical eligibility criteria for contraceptive use. 6th ed. Geneva: World Health Organization; 2025.
- Polakow-Farkash, S., Gilad, O., Merlob, P., Stahl, B., Yogev, Y., & Klinger, G. (2013). Levonorgestrel used for emergency contraception during lactation-a prospective observational cohort study on maternal and infant safety. The Journal of Maternal-Fetal & Neonatal Medicine: The Official Journal of the European Association of Perinatal Medicine, the Federation of Asia and Oceania Perinatal Societies, the International Society of Perinatal Obstetricians, 26(3), 219–221.
- Progestogen-only contraceptives during lactation: I. Infant growth. World Health Organization Task force for Epidemiological Research on Reproductive Health; Special Programme of Research, Development and Research Training in Human Reproduction. (1994). Contraception, 50(1), 35–53.
- Sausjord IK, Acton LW, White KO, O’Connor SK, Lerner NM. Breastfeeding and hormonal contraception: a scoping review of clinical guidelines, professional association recommendations, and the literature. Breastfeed Med. 2023;18(9):645-665.
- Segev L, Ben Zimra A, Weitzman GA, Bloch N, Pitussi I, Alkhazov T, et al. Ethinylestradiol transfer into breast milk of women using low-dose combined hormonal contraception is negligible. Open Access J Contracept. 2025;16:189-197.
- Shaaban, O. M., Abbas, A. M., Mahmoud, H. R., Yones, E. M., Mahmoud, A., & Zakherah, M. S. (2019). Levonorgestrel emergency contraceptive pills use during breastfeeding, effect on infants’ health and development. The Journal of Maternal-Fetal & Neonatal Medicine: The Official Journal of the European Association of Perinatal Medicine, the Federation of Asia and Oceania Perinatal Societies, the International Society of Perinatal Obstetricians, 32(15), 2524–2528.
- Shaaban, O. M., Hassen, S. G., Nour, S. A., Kames, M. A., & Yones, E. M. (2013). Emergency contraceptive pills as a backup for lactational amenorrhea method (LAM) of contraception: a randomized controlled trial. Contraception, 87(3), 363–369.
- Shaamash, A. H., Sayed, G. H., Hussien, M. M., & Shaaban, M. M. (2005). A comparative study of the levonorgestrel-releasing intrauterine system Mirena versus the Copper T380A intrauterine device during lactation: breast-feeding performance, infant growth and infant development. Contraception, 72(5), 346–351.
- Specialist Pharmacy Service. Using emergency contraception during breastfeeding [Internet]. 2023.
- The World Health Organization multinational study of breast-feeding and lactational amenorrhea. III. Pregnancy during breast-feeding. World Health Organization Task Force on Methods for the Natural Regulation of Fertility. (1999). Fertility and Sterility, 72(3), 431–440.
- The World Health Organization multinational study of breast-feeding and lactational amenorrhea. IV. Postpartum bleeding and lochia in breast-feeding women. World Health Organization Task Force on Methods for the Natural Regulation of Fertility. (1999). Fertility and Sterility, 72(3), 441–447.
- WHO? Department of Reproductive Health and Research World Health Organization. Medical Eligibility Criteria for Contraceptive Use. WHO/RHR/15.07. 2015. (s/f).
- Wijden C, V., J, K., & Berk T, V. (2003). Lactational amenorrhea for family planning. Cochrane Database Syst Rev, 4) :CD001329.
- ACOG - American College of Obstetricians and Gynecologists Vaccinating Pregnant and Lactating Patients Against COVID-19. ACOG 2020/12/13
- AELAMA (Asociación Española de Lactancia Materna). Gómez Fernández-Vegue, M. Consideraciones acerca de las vacunas frente a la COVID-19 y la lactancia materna.2021
- Akamine Y, Fujiyama N, Kagaya H, Saito M, Miura H, Terada Y, Takahashi T, Satoh S, Miura M. Tacrolimus concentrations after renal transplantation in a mother-neonate dyad: Maternal, neonatal and breast milk measurements. J Clin Pharm Ther. 2021 Dec;46(6):1800-1803
- Amir, L. H., Pirotta, M. V., & Raval, M. (2011). Breastfeeding--evidence based guidelines for the use of medicines. Australian Family Physician, 40(9), 684–690.
- Arbex, M. A., Varella, M. de C. L., Siqueira, H. R. de, & Mello, F. A. F. de. (2010). Drogas antituberculose: interações medicamentosas, efeitos adversos e utilização em situações especiais - parte 2: fármacos de segunda linha. Jornal brasileiro de pneumologia: publicacao oficial da Sociedade Brasileira de Pneumologia e Tisilogia, 36(5), 641–656.
- Athavale, M. A., Maitra, A., Patel, S., Bhate, V. R., & Toddywalla, V. S. (2013). Development of an in vitro cell culture model to study milk to plasma ratios of therapeutic drugs. Indian Journal of Pharmacology, 45(4), 325–329.
- Bailey, D. N., Weibert, R. T., Naylor, A. J., & Shaw, R. F. (1982). A study of salicylate and caffeine excretion in the breast milk of two nursing mothers. Journal of Analytical Toxicology, 6(2), 64–68.
- Baird, J. K., Jensen, S. M., Urba, W. J., Fox, B. A., & Baird, J. R. (2021). SARS-CoV-2 antibodies detected in human breast milk post-vaccination. doi :10.1101/2021.02.23.21252328
- Baker, T. E., Cooper, S. D., Kessler, L., & Hale, T. W. (2015). Transfer of natalizumab into breast milk in a mother with multiple sclerosis. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 31(2), 233–236.
- Bar-Oz, B., Bulkowstein, M., Benyamini, L., Greenberg, R., Soriano, I., Zimmerman, D., … Berkovitch, M. (2003). Use of antibiotic and analgesic drugs during lactation. Drug Safety: An International Journal of Medical Toxicology and Drug Experience, 26(13), 925–935.
- Bell, A. D., Roussin, A., Cartier, R., Chan, W. S., Douketis, J. D., Gupta, A., … Tanguay, J.-F. (2011). The use of antiplatelet therapy in the outpatient setting: Canadian Cardiovascular Society Guidelines Executive Summary. The Canadian Journal of Cardiology, 27(2), 208–221.
- Bloor, M., & Paech, M. (2013). Nonsteroidal anti-inflammatory drugs during pregnancy and the initiation of lactation. Anesthesia and Analgesia, 116(5), 1063–1075.
- Bourget, P., Quinquis-Desmaris, V., & Fernandez, H. (1993). Ceftriaxone distribution and protein binding between maternal blood and milk postpartum. The Annals of Pharmacotherapy, 27(3), 294–297.
- Breastfeeding and Maternal Medication. Recommendations for Drugs in the Eleventh WHO Model List of Essential Drugs. 2002.
- Breyer-Pfaff, U., Nill, K., Entenmann, K. N., & Gaertner, H. J. (1995). Secretion of amitriptyline and metabolites into breast milk. The American Journal of Psychiatry, 152(5), 812–813.
- Brixen-Rasmussen, L., Halgrener, J., & Jørgensen, A. (1982). Amitriptyline and nortriptyline excretion in human breast milk. Psychopharmacology, 76(1), 94–95.
- CDC 2020/02/04. Vaccinations. https://www.cdc.gov/breastfeeding/breastfeeding-special-circumstances/vaccinations-medications-drugs/vaccinations.html" target="_blank">https://www.cdc.gov/breastfeeding/breastfeeding-special-circumstances/vaccinations-medications-drugs/vaccinations.html" target="_blank">https://www.cdc.gov/breastfeeding/breastfeeding-special-circumstances/vaccinations-medications-drugs/vaccinations.html
- CDC 2020/12/13. Vaccine Recommendations. https://www.cdc.gov/vaccines/hcp/acip-recs/vacc-specific/covid-19.html" target="_blank">https://www.cdc.gov/vaccines/hcp/acip-recs/vacc-specific/covid-19.html" target="_blank">https://www.cdc.gov/vaccines/hcp/acip-recs/vacc-specific/covid-19.html
- CDC 2020/12/18 (2021a, junio 29). Información para entender cómo actúan las vacunas contra el COVID-19.: https://espanol.cdc.gov/coronavirus/2019-ncov/vaccines/different-vaccines/how-they-work.html?CDC_AA_refVal=https%3A%2F%2Fwww.cdc.gov%2Fcoronavirus%2F2019-ncov%2Fvaccines%2Fabout-vaccines%2Fhow-they-work.html" target="_blank">https://espanol.cdc.gov/coronavirus/2019-ncov/vaccines/different-vaccines/how-they-work.html?CDC_AA_refVal=https%3A%2F%2Fwww.cdc.gov%2Fcoronavirus%2F2019-ncov%2Fvaccines%2Fabout-vaccines%2Fhow-they-work.html" target="_blank">https://espanol.cdc.gov/coronavirus/2019-ncov/vaccines/different-vaccines/how-they-work.html?CDC_AA_refVal=https%3A%2F%2Fwww.cdc.gov%2Fcoronavirus%2F2019-ncov%2Fvaccines%2Fabout-vaccines%2Fhow-they-work.html
- CDC. (2021, septiembre 7). COVID-19 vaccines while pregnant or breastfeeding. Recuperado el 16 de septiembre de 2021, de Cdc.gov website: https://www.cdc.gov/coronavirus/2019-ncov/vaccines/recommendations/pregnancy.html" target="_blank">https://www.cdc.gov/coronavirus/2019-ncov/vaccines/recommendations/pregnancy.html" target="_blank">https://www.cdc.gov/coronavirus/2019-ncov/vaccines/recommendations/pregnancy.html
- Chen, L. H., Zeind, C., Mackell, S., LaPointe, T., Mutsch, M., & Wilson, M. E. (2010). Breastfeeding travelers : precautions and recommendations. Journal of Travel Medicine, 17(1), 32–47.
- Chervenak, F. A., McCullough, L. B., Bornstein, E., Johnson, L., Katz, A., McLeod-Sordjan, R., Grünebaum, A. (2021). Professionally responsible coronavirus disease 2019 vaccination counseling of obstetrical and gynecologic patients. American Journal of Obstetrics and Gynecology, 224(5), 470–478.
- Chin, K. G., McPherson, C. E., 3rd, Hoffman, M., Kuchta, A., & Mactal-Haaf, C. (2001). Use of anti-infective agents during lactation : Part 2--Aminoglycosides, macrolides, quinolones, sulfonamides, trimethoprim, tetracyclines, chloramphenicol, clindamycin, and metronidazole. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 17(1), 54–65.
- Chiu, T.-M., Chu, Y.-N., Lee, M.-S., Yang, S.-C., Tai, H.-C., & Chung, W.-H. (2019). Toxic epidermal necrolysis in an infant induced by drug intake through breast milk. Dermatologica Sinica, 37(2), 86.
- Chowdhury, R., Sinha, B., Sankar, M. J., Taneja, S., Bhandari, N., Rollins, N., Martines, J. (2015). Breastfeeding and maternal health outcomes: a systematic review and meta-analysis. Acta Paediatrica (Oslo, Norway: 1992), 104, 96–113.
- Ciplea, A. I., Langer-Gould, A., de Vries, A., Schaap, T., Thiel, S., Ringelstein, M., Hellwig, K. (2020). Monoclonal antibody treatment during pregnancy and/or lactation in women with MS or neuromyelitis optica spectrum disorder. Neurology(R) Neuroimmunology & Neuroinflammation, 7(4), e723.
- Clark, J. H., & Wilson, W. G. (1981). A 16-day-old breast-fed infant with metabolic acidosis caused by salicylate. Clinical Pediatrics, 20(1), 53–54.
- Collier, A.-R. Y., McMahan, K., Yu, J., Tostanoski, L. H., Aguayo, R., Ansel, J., Barouch, D. H. (2021). Immunogenicity of COVID-19 mRNA vaccines in pregnant and lactating women. JAMA : The Journal of the American Medical Association, 325(23), 2370–2380.
- Constantinescu, S., Pai, A., Coscia, L. A., Davison, J. M., Moritz, M. J., & Armenti, V. T. (2014). Breast-feeding after transplantation. Best Practice & Research. Clinical Obstetrics & Gynaecology, 28(8), 1163–1173.
- Costantine, M. M., Landon, M. B., & Saade, G. R. (2020). Protection by exclusion: Another missed opportunity to include pregnant women in research during the Coronavirus disease 2019 (COVID-19) pandemic. Obstetrics and Gynecology, 136(1), 26–28.
- COVID-19 Vaccine in Pregnancy and Breastfeeding. (s/f). Recuperado el 16 de septiembre de 2021, de Infantrisk.com website: https://www.infantrisk.com/covid-19-vaccine-pregnancy-and-breastfeeding" target="_blank">https://www.infantrisk.com/covid-19-vaccine-pregnancy-and-breastfeeding" target="_blank">https://www.infantrisk.com/covid-19-vaccine-pregnancy-and-breastfeeding
- COVID-19 vaccine tracker and landscape. (s/f). Recuperado el 16 de septiembre de 2021, de Who.int website: https://www.who.int/publications/m/item/draft-landscape-of-covid-19-candidate-vaccines" target="_blank">https://www.who.int/publications/m/item/draft-landscape-of-covid-19-candidate-vaccines" target="_blank">https://www.who.int/publications/m/item/draft-landscape-of-covid-19-candidate-vaccines
- Datta, P., Rewers-Felkins, K., Kallem, R. R., Baker, T., & Hale, T. W. (2017). Transfer of low dose aspirin into human milk. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 33(2), 296–299.
- Davanzo, R., Agosti, M., Cetin, I., Chiantera, A., Corsello, G., Ramenghi, L. A., Mosca, F. (2021). Breastfeeding and COVID-19 vaccination: position statement of the Italian scientific societies. Italian Journal of Pediatrics, 47(1), 45.
- Davanzo, R., Bua, J., Paloni, G., & Facchina, G. (2014). Breastfeeding and migraine drugs. European Journal of Clinical Pharmacology, 70(11), 1313–1324.
- Dodd, S., Stocky, A., Buist, A., Burrows, G. D., & Norman, T. R. (2001). Sertraline analysis in the plasma of breast-fed infants. The Australian and New Zealand Journal of Psychiatry, 35(4), 545–546.
- Durst, J. K., & Rampersad, R. M. (2015). Pregnancy in women with solid-organ transplants: A review: A review. Obstetrical & Gynecological Survey, 70(6), 408–418.
- EBCOG. Martins I, Louwen F, Ayres-de-Campos D, Mahmood T. EBCOG position statement on COVID-19 vaccination for pregnant and breastfeeding women. Eur J Obstet Gynecol Reprod Biol. 2021 May 14. pii: S0301-2115(21)00244-X.
- Edmonds, C. E., Zuckerman, S. P., & Conant, E. F. (2021). Management of unilateral axillary lymphadenopathy detected on breast MRI in the era of COVID-19 vaccination. AJR. American Journal of Roentgenology, (AJR.21.25604), 1–4.
- Ellsworth, A. (1994). Pharmacotherapy of asthma while breastfeeding. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 10(1), 39–41.
- French, A. E., Soldin, S. J., Soldin, O. P., & Koren, G. (2003). Milk transfer and neonatal safety of tacrolimus. The Annals of Pharmacotherapy, 37(6), 815–818.
- Götestam Skorpen, C., Hoeltzenbein, M., Tincani, A., Fischer-Betz, R., Elefant, E., Chambers, C., … Østensen, M. (2016). The EULAR points to consider for use of antirheumatic drugs before pregnancy, and during pregnancy and lactation. Annals of the Rheumatic Diseases, 75(5), 795–810.
- Graf, H., & Riemann, S. (1959). Untersuchungen über die Konzentration von Pyrrolidino-methyl-tetracyclin1in der Muttermilch. Deutsche medizinische Wochenschrift (1946), 84(37), 1694–1697.
- Gray, K. J., Bordt, E. A., Atyeo, C., Deriso, E., Akinwunmi, B., Young, N., Edlow, A. G. (2021). Coronavirus disease 2019 vaccine response in pregnant and lactating women: a cohort study. American Journal of Obstetrics and Gynecology, 225(3), 303.e1-303.e17.
- Grzeskowiak, L. E., Leggett, C., Costi, L., Roberts, C. T., & Amir, L. H. (2018). Impact of serotonin reuptake inhibitor use on breast milk supply in mothers of preterm infants: a retrospective cohort study. British Journal of Clinical Pharmacology, 84(6), 1373–1379.
- Hägg, S., & Spigset, O. (2000). Anticonvulsant uses during lactation. Drug Safety: An International Journal of Medical Toxicology and Drug Experience, 22(6), 425–440.
- Harley, J. D., & Robin, H. (1962). “late” neonatal jaundice in infants with glucose-6-phosphate dehydrogenase-deficient erythrocytes. Australasian Annals of Medicine, 11(3), 148–155.
- Hendrick, V., Fukuchi, A., Altshuler, L., Widawski, M., Wertheimer, A., & Brunhuber, M. V. (2001). Use of sertraline, paroxetine, and fluvoxamine by nursing women. The British Journal of Psychiatry: The Journal of Mental Science, 179, 163–166.
- Hendrick, V., Smith, L. M., Hwang, S., Altshuler, L. L., & Haynes, D. (2003). Weight gain in breastfed infants of mothers taking antidepressant medications. The Journal of Clinical Psychiatry, 64(4), 410–412.
- Holland, D. (2000). An observation of the effect of sertraline on breast milk supply. The Australian and New Zealand Journal of Psychiatry, 34(6), 1032.
- IHAN. Iniciativa para la Humanización de la Asistencia al Nacimiento y la Lactancia. Comunicado IHAN: vacunación frente a COVID-19 y lactancia materna. 2021
- Ilett, K. F., Hackett, L. P., Ingle, B., & Bretz, P. J. (2006). Transfer of probenecid and cephalexin into breast milk. The Annals of Pharmacotherapy, 40(5), 986–989.
- Iqbal, M. M., Sobhan, T., & Ryals, T. (2002). Effects of commonly used benzodiazepines on the fetus, the neonate, and the nursing infant. Psychiatric Services (Washington, D.C.), 53(1), 39–49.
- Ito, S., Blajchman, A., Stephenson, M., Eliopoulos, C., & Koren, G. (1993). Prospective follow-up of adverse reactions in breast-fed infants exposed to maternal medication. American Journal of Obstetrics and Gynecology, 168(5), 1393–1399.
- Jahanfar, S., Ng, C. J., & Teng, C. L. (2013). Antibiotics for mastitis in breastfeeding women. Cochrane Database of Systematic Reviews, (2), CD005458.
- Janssen, N. M., & Genta, M. S. (2000). The effects of immunosuppressive and anti-inflammatory medications on fertility, pregnancy, and lactation. Archives of Internal Medicine, 160(5), 610–619.
- Kafetzis, D. A., Siafas, C. A., Georgakopoulos, P. A., & Papadatos, C. J. (1981). Passage of cephalosporins and amoxicillin into the breast milk. Acta Paediatrica Scandinavica, 70(3), 285–288.
- Kelly, J. C., Carter, E. B., Raghuraman, N., Nolan, L. S., Gong, Q., Lewis, A. N., & Good, M. (2021). Anti-severe acute respiratory syndrome coronavirus 2 antibodies induced in breast milk after Pfizer-BioNTech/BNT162b2 vaccination. American Journal of Obstetrics and Gynecology, 225(1), 101–103.
- Kelly, L. E., Poon, S., Madadi, P., & Koren, G. (2012). Neonatal benzodiazepines exposure during breastfeeding. The Journal of Pediatrics, 161(3), 448–451.
- Kociszewska-Najman, B., Mazanowska, N., Pietrzak, B., Paczek, L., Szpotanska-Sikorska, M., Schreiber-Zamora, J., … Wielgos, M. (2018). Low transfer of tacrolimus and its metabolites into colostrum of graft recipient mothers. Nutrients, 10(3). Doi :10.3390/nu10030267
- Kuczaj A, Danel A, Warwas S, Przybyłowski P, Śliwka J, Pawlak S, Trzcińska I, Hrapkowicz T. Toxic milk- should we still be afraid of breastfeeding while on tacrolimus therapy: A case study. J Heart Lung Transplant 2024;43:S631.
- Leggett, C., Costi, L., Morrison, J. L., Clifton, V. L., & Grzeskowiak, L. E. (2017). Antidepressant use in late gestation and breastfeeding rates at discharge from hospital. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 33(4), 701–709.
- Lesaca, T. G. (1996). Sertraline and galactorrhea. Journal of Clinical Psychopharmacology, 16(4), 333–334.
- Malcova, H., Sumnik, Z., Drevinek, P., Venhacova, J., Lebl, J., & Cinek, O. (2006). Absence of breast-feeding is associated with the risk of type 1 diabetes: a case-control study in a population with rapidly increasing incidence. European Journal of Pediatrics, 165(2), 114–119.
- Matias, S. L., Dewey, K. G., Quesenberry, C. P., Jr, & Gunderson, E. P. (2014). Maternal prepregnancy obesity and insulin treatment during pregnancy are independently associated with delayed lactogenesis in women with recent gestational diabetes mellitus. The American Journal of Clinical Nutrition, 99(1), 115–121.
- Matsuda, S. (1984). Transfer of antibiotics into maternal milk. Biological Research in Pregnancy and Perinatology, 5(2), 57–60.
- Mayo, S., & Monfort, S. (2021). Letter to the editor: Breastfeeding and COVID-19 vaccine: Yes, we can. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 37(2), 275–276.
- Mazzuoccolo, L. D., Andrada, R., Pellerano, G., Neglia, V., & Abeldaño, A. (2014). Levels of cyclosporine in breast milk and passage into the circulation of the infant of a mother with psoriasis: Cyclosporine in breast milk. International Journal of Dermatology, 53(3), 355–356.
- McLaurin-Jiang, S., Garner, C. D., Krutsch, K., & Hale, T. W. (2021). Maternal and child symptoms following COVID-19 vaccination among breastfeeding mothers. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine. doi:10.1089/bfm.2021.0079
- Mehta, N., Sales, R. M., Babagbemi, K., Levy, A. D., McGrath, A. L., Drotman, M., & Dodelzon, K. (2021). Unilateral axillary Adenopathy in the setting of COVID-19 vaccine. Clinical Imaging, 75, 12–15.
- Mitchell KB, Johnson HM, Rodríguez JM, Eglash A, Scherzinger C, Zakarija-Grkovic I, et al. Academy of Breastfeeding Medicine Clinical Protocol #36: The Mastitis Spectrum, Revised 2022. Breastfeed Med. 2022;17(5):360-376. doi:10.1089/bfm.2022.29207.kbm.
- Morton, A. (2011). Cyclosporine and lactation: Correspondence. Nephrology (Carlton, Vic.), 16(2), 249.
- Müller, M. J., Preuß, C., Paul, T., Streit, F., Brandhorst, G., & Seeliger, S. (2013). Serotonergic overstimulation in a preterm infant after sertraline intake via breastmilk. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 8(3), 327–329.
- National Asthma Education and Prevention Program Asthma and Pregnancy Working Group. Managing asthma during pregnancy : recommendations for pharmacologic treatment-2004 update. 2004 ;1-57. 2004. (2004).
- Nebhinani, N. (2013). Sertraline-induced galactorrhea: case report and review of cases reported with other SSRIs. General Hospital Psychiatry, 35(5), 576.e3-5.
- Nice, Frank J., DeEugenio, D., DiMino, T. A., Freeny, I. C., Rovnack, M. B., & Gromelski, J. S. (2004). Medications and breast-feeding: A guide for pharmacists, pharmacy technicians, and other healthcare professionals part I. The Journal of Pharmacy Technology: JPT: Official Publication of the Association of Pharmacy Technicians, 20(1), 17–27.
- O’Reilly, M. W., Avalos, G., Dennedy, M. C., O’Sullivan, E. P., & Dunne, F. (2011). Atlantic DIP: high prevalence of abnormal glucose tolerance post-partum is reduced by breast-feeding in women with prior gestational diabetes mellitus. European Journal of Endocrinology, 165(6), 953–959.
- OMS. Interim recommendations for use of the Moderna mRNA-1273 vaccine against COVID-19. website: https://www.who.int/publications/i/item/interim-recommendations-for-use-of-the-moderna-mrna-1273-vaccine-against-covid-19" target="_blank">https://www.who.int/publications/i/item/interim-recommendations-for-use-of-the-moderna-mrna-1273-vaccine-against-covid-19" target="_blank">https://www.who.int/publications/i/item/interim-recommendations-for-use-of-the-moderna-mrna-1273-vaccine-against-covid-19
- Østensen, M., Khamashta, M., Lockshin, M., Parke, A., Brucato, A., Carp, H., … Tincani, A. (2006). Anti-inflammatory and immunosuppressive drugs and reproduction. Arthritis Research & Therapy, 8(3), 209.
- Palacios, R., Patiño, E. G., de Oliveira Piorelli, R., Conde, M. T. R. P., Batista, A. P., Zeng, G., … Gast, C. (2020). Double-Blind, Randomized, Placebo-Controlled Phase III Clinical Trial to Evaluate the Efficacy and Safety of treating Healthcare Professionals with the Adsorbed COVID-19 (Inactivated) Vaccine Manufactured by Sinovac - PROFISCOV: A structured summary of a study protocol for a randomised controlled trial. Trials, 21(1), 853.
- Paricio-Talayero, J. M., Mena-Tudela, D., & Cervera-Gasch, Á. (2020). Is it compatible with breastfeeding? www. E-lactancia. org: Analysis of visits, user profile and most visited products [published online ahead of print. Int J Med Inform, 141(104199).
- Perl, S. H., Uzan-Yulzari, A., Klainer, H., Asiskovich, L., Youngster, M., Rinott, E., & Youngster, I. (2021). SARS-CoV-2-specific antibodies in breast milk after COVID-19 vaccination of breastfeeding women. JAMA: The Journal of the American Medical Association, 325(19), 2013–2014.
- Petit, A., Piednoir, D., Germain, M.-L., & Trenque, T. (2003). Drug-induced hyperprolactinemia: à case-non-case study from the national pharmacovigilance database. Therapie, 58(2), 159–163.
- Pogliani, L., Baldelli, S., Cattaneo, D., Pileri, P., Clementi, E., Cetin, I., & Zuccotti, G. (2019). Selective serotonin reuptake inhibitors’ passage into human milk of lactating women. The Journal of Maternal-Fetal & Neonatal Medicine: The Official Journal of the European Association of Perinatal Medicine, the Federation of Asia and Oceania Perinatal Societies, the International Society of Perinatal Obstetricians, 32(18), 3020–3025.
- Posner, A. C., Prigot, A., & Konicoff, N. G. (s/f). Further observations on the use of tetracycline hydrochloride in prophylaxis and treatment of obstetric infections.
- Prakash, O., Mathur, G. P., Kushwaha, K. P., & Singh, Y. D. (1990). Drug exposure in pregnant and lactating mothers in periurban areas. Indian Pediatrics, 27(12), 1301–1302.
- Ramìreza, D. S. R., Pérez, M. M. L., Pérez, M. C., Isis, M., Hernández, S., Hospital, S. M. P., Bello, M. Á. G. (2021). SARS-CoV-2 antibodies in breast milk after vaccination. Pediatrics, e2021052286.
- Risser, A., Donovan, D., Heintzman, J., & Page, T. (2009). NSAID prescribing precautions. American Family Physician, 80(12), 1371–1378.
- Rubin, E. T., Lee, A., & Ito, S. (2004). When breastfeeding mothers need CNS-acting drugs. Journal Canadien de Pharmacologie Clinique [The Canadian Journal of Clinical Pharmacology], 11(2), e257-66.
- Sadauskaite-Kuehne, V., Ludvigsson, J., Padaiga, Z., Jasinskiene, E., & Samuelsson, U. (2004). Longer breastfeeding is an independent protective factor against development of type 1 diabetes mellitus in childhood. Diabetes/Metabolism Research and Reviews, 20(2), 150–157.
- Salazar, F. R., D’Avila, F. B., de Oliveira, M. H., Ferreira, P. L., & Bergold, A. M. (2016). Development and validation of a bioanalytical method for five antidepressants in human milk by LC-MS. Journal of Pharmaceutical and Biomedical Analysis, 129, 502–508.
- Saus-Ortega, C. (2021). Letter to the editor: COVID-19 vaccines and breastfeeding. Journal of Human Lactation: Official Journal of International Lactation Consultant Association, 37(2), 273–274.
- Schaefer, C. (2015). Drugs during pregnancy and lactation: Treatment options and risk assessment (3a ed.). San Diego, CA, Estados Unidos de América: Academic Press.
- Schiaffino S, Pinker K, Cozzi A, Magni V, Athanasiou A, Baltzer PAT, et al. European Society of Breast Imaging (EUSOBI) guidelines on the management of axillary lymphadenopathy after COVID-19 vaccination: 2023 revision. Insights Imaging. 2023;14(1):126. doi:10.1186/s13244-023-01453-2.
- Schoretsanitis, G., Augustin, M., Saßmannshausen, H., Franz, C., Gründer, G., & Paulzen, M. (2019). Antidepressants in breast milk; comparative analysis of excretion ratios. Archives of Women’s Mental Health, 22(3), 383–390.
- Shepherd E, Grivell RM. Aspirin (single dose) for perineal pain in the early postpartum period. Cochrane Database Syst Rev. 2020 Jul 24;7(7):CD012129ç
- Spigset, O., & H ??gg, S. (2000). Analgesics and breast-feeding: Safety considerations. Paediatric Drugs, 2(3), 223–238.
- Stowe, Z. N., Hostetter, A. L., Owens, M. J., Ritchie, J. C., Sternberg, K., Cohen, L. S., & Nemeroff, C. B. (2003). The pharmacokinetics of sertraline excretion into human breast milk: Determinants of infant serum concentrations. The journal of clinical psychiatry, 64(1), 73–80.
- Stowe, Z. N., Owens, M. J., Landry, J. C., Kilts, C. D., Ely, T., Llewellyn, A., & Nemeroff, C. B. (1997). Sertraline and desmethylsertraline in human breast milk and nursing infants. The American Journal of Psychiatry, 154(9), 1255–1260.
- Terragna, A., & Spirito, L. (1967). Thrombocytopenic purpura in an infant after administration of acetylsalicylic acid to the wet-nurse. Minerva pediatrica, 19(13), 613–616.
- Thiagarajan, K. M.-F., Arakali, S. R., Mealey, K. J., Cardonick, E. H., Gaughan, W. J., Davison, J. M., Armenti, V. T. (2013). Safety considerations: breastfeeding after transplant. Progress in Transplantation (Aliso Viejo, Calif.), 23(2), 137–146.
- Trenque, T., Herlem, E., Auriche, P., & Dramé, M. (2011). Serotonin reuptake inhibitors and hyperprolactinaemia: à case/non-case study in the French pharmacovigilance database: A case/non-case study in the french pharmacovigilance database. Drug Safety: An International Journal of Medical Toxicology and Drug Experience, 34(12), 1161–1166.
- Uguz, F. (2021). A new safety scoring system for the use of psychotropic drugs during lactation. American Journal of Therapeutics, 28(1), e118–e126.
- Unsworth, J., d’Assis-Fonseca, A., Beswick, D. T., & Blake, D. R. (1987). Serum salicylate levels in a breast fed infant. Annals of the Rheumatic Diseases, 46(8), 638–639.
- Valcarce, V., Stafford, L. S., Neu, J., Cacho, N., Parker, L., Mueller, M., … Larkin, J., 3rd. (2021). Detection of SARS-CoV-2-specific IgA in the human milk of COVID-19 vaccinated lactating health care workers. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine. doi:10.1089/bfm.2021.0122
- Van der Woude, C. Janneke, Kolacek, S., Dotan, I., Oresland, T., Vermeire, S., Munkholm, P., … European Crohn’s Colitis Organisation (ECCO). (2010). European evidenced-based consensus on reproduction in inflammatory bowel disease. Journal of Crohn’s & Colitis, 4(5), 493–510.
- Van Wattum, J. J., Leferink, T. M., Wilffert, B., & ter Horst, P. G. J. (2019). Antibiotics and lactation: An overview of relative infant doses and a systematic assessment of clinical studies. Basic & Clinical Pharmacology & Toxicology, 124(1), 5–17.
- Weisskopf, E., Panchaud, A., Nguyen, K. A., Grosjean, D., Hascoët, J.-M., Csajka, C., collaborators of the SSRI-Breast Milk study. (2017). Simultaneous determination of selective serotonin reuptake inhibitors and their main metabolites in human breast milk by liquid chromatography-electrospray mass spectrometry. Journal of Chromatography. B, Analytical Technologies in the Biomedical and Life Sciences, 1057, 101–109.
- Whittam, D. H., Tallantyre, E. C., Jolles, S., Huda, S., Moots, R. J., Kim, H. J., … Jacob, A. (2019). Rituximab in neurological disease: principles, evidence and practice. Practical Neurology, 19(1), 5–20.
- Wisner, K. L., Perel, J. M., & Findling, R. L. (1996). Antidepressant treatment during breast-feeding. The American Journal of Psychiatry, 153(9), 1132–1137.
- Wisner, Katherine L., Hanusa, B. H., Perel, J. M., Peindl, K. S., Piontek, C. M., Sit, D. K. Y., Moses-Kolko, E. L. (2006). Postpartum depression: a randomized trial of sertraline versus nortriptyline: A randomized trial of sertraline versus nortriptyline. Journal of Clinical Psychopharmacology, 26(4), 353–360.
- Wright, A. L., Stern, D. A., & Halonen, M. (2001). The association of allergic sensitization in mother and child in breast-fed and formula-fed infants. Advances in Experimental Medicine and Biology, 501, 249–255.
- Yoshida, K., Smith, B., Craggs, M., & Kumar, R. C. (1997). Investigation of pharmacokinetics and of possible adverse effects in infants exposed to tricyclic antidepressants in breast milk. Journal of Affective Disorders, 43(3), 225–237.
- Administration of Radioactive Substances Advisory Committee. ARSAC. Notes for guidance on the clinical administration of radiopharmaceuticals and use of sealed radioactive sources. March 2025
- American College of Radiology. Manual on Contrast Media [Internet]. Reston (VA): American College of Radiology; 2025 [citado 2026 abr 16]. Disponible en: https://www.acr.org/Clinical-Resources/Clinical-Tools-and-Reference/Contrast-Manual" target="_blank">https://www.acr.org/Clinical-Resources/Clinical-Tools-and-Reference/Contrast-Manual" target="_blank">https://www.acr.org/Clinical-Resources/Clinical-Tools-and-Reference/Contrast-Manual?utm_source=chatgpt.com" target="_blank">https://www.acr.org/Clinical-Resources/Clinical-Tools-and-Reference/Contrast-Manual?utm_source=chatgpt.com">https://www.acr.org/Clinical-Resources/Clinical-Tools-and-Reference/Contrast-Manual
- American College of Radiology. ACR Appropriateness Criteria® Breast Imaging of Lactating Women [Internet]. Reston (VA): American College of Radiology;
- American Society of Breast Surgeons. Resource Guide on Oncolactation [Internet]. 2024
- American Society of Anesthesiologists. Statement on resuming breastfeeding after anesthesia [Internet].
- Bettmann MA. Frequently asked questions: iodinated contrast agents. Radiographics. 2004;24 Suppl 1:S3-S10.
- Hale TW, Rowe HE. Medications and Mothers’ Milk 2017. 17th ed. New York: Springer Publishing Company; 2016.
- Howe DB, Beardsley M, Bakhsh S. Consolidated Guidance About Materials Licenses: Program-Specific Guidance About Medical Use Licenses. Vol 9. Washington, DC: U.S. Nuclear Regulatory Commission; 2008.
- Mitchell KB, Fleming MM, Anderson PO, Giesbrandt JG. ABM Clinical Protocol #31: Radiology and Nuclear Medicine Studies in Lactating Women. Breastfeed Med. 2019;14(5):290-4.
- Moretti ME, Lee A, Ito S. Which drugs are contraindicated during breastfeeding? Practice guidelines. Can Fam Physician. 2000;46:1753-7.
- Mountford, P. J., & O’Doherty, M. J. (1999). Exposure of critical groups to nuclear medicine patients. Applied Radiation and Isotopes: Including Data, Instrumentation and Methods for Use in Agriculture, Industry and Medicine, 50(1), 89–111.
- Siegel, J. (2002). Guide for Diagnostic Nuclear Medicine. Nuclear Regulatory Commission Regulation of Nuclear Medicine; 2002. Available at https://www.nrc.gov/materials/miau/miaureg-initiatives/guide_2002.pdf" target="_blank">https://www.nrc.gov/materials/miau/miaureg-initiatives/guide_2002.pdf" target="_blank">https://www.nrc.gov/materials/miau/miaureg-initiatives/guide_2002.pdf (accessed November 1, 2018). Recuperado el 15 de septiembre de 2002, de Nrc.gov website: https://www.nrc.gov/materials/miau/miaureg-initiatives/guide_2002.pdf" target="_blank">https://www.nrc.gov/materials/miau/miaureg-initiatives/guide_2002.pdf" target="_blank">https://www.nrc.gov/materials/miau/miaureg-initiatives/guide_2002.pdf
- Tremblay, E., Thérasse, E., Thomassin-Naggara, I., & Trop, I. (2012). Quality initiatives: guidelines for use of medical imaging during pregnancy and lactation. Radiographics: A Review Publication of the Radiological Society of North America, Inc, 32(3), 897–911.
- Webb, J. A., Thomsen, H. S., & Morcos, S. K. (2005). Members of Contrast Media Safety Committee of European Society of Urogenital Radiology (ESUR). The use of iodinated and gadolinium contrast media during pregnancy and lactation. Eur Radiol.
- Brodribb W. ABM Clinical Protocol #9: Use of Galactogogues in Initiating or Augmenting Maternal Milk Production, Second Revision 2018. Breastfeed Med. 2018 Jun ;13(5) :307-314.
- Cragg A, Levene I, Darabi S, Willcox M. Herbal galactagogues to improve breastmilk production and lactation in mothers of preterm babies: a systematic review of clinical trials. Eur J Clin Nutr. 2026;80(2):146-158. doi:10.1038/s41430-025-01679-x.
- Erarslan ZB, Kültür Ş. Medicinal plants traditionally used to increase breast milk in Turkey: an ethnobotanical review. J Herbal Med. 2024;44:100849. doi:10.1016/j.hermed.2024.100849.
- Foong SC, Tan ML, Foong WC, Marasco LA, Ho JJ, Ong JH. Oral galactagogues (natural therapies or drugs) for increasing breast milk production in mothers of non-hospitalised term infants. Cochrane Database Syst Rev. 2020;5(5):CD011505. doi:10.1002/14651858.CD011505.pub2.
- Hussain NHN, Noor NM, Ismail SB, Zainuddin NA, Sulaiman Z. Metoclopramide for milk production in lactating women: a systematic review and meta-analysis. Korean J Fam Med. 2021;42(6):453-463.
- Metoclopramide. In: Drugs and Lactation Database (LactMed®) [Internet]. Bethesda (MD): National Institute of Child Health and Human Development; 2006-. Updated 2026 Feb 15. Available from: NCBI Bookshelf.
- National Center for Complementary and Integrative Health (NCCIH). Fenugreek: Usefulness and Safety [Internet]. Bethesda (MD): National Center for Complementary and Integrative Health; 2025.
- Rosti L, Nardini A, Bettinelli ME, Rosti D. Toxic effects of a herbal tea mixture in two newborns. Acta Paediatr. 1994 jun;83(6):683
- Şahin B, Kaymaz N, Yıldırım Ş. Herbal remedies for perceived inadequate milk supply are not as safe as women think A brief case report. Women Birth. 2016 Dec;29(6): e133.
- Shen Q, Khan KS, Du MC, Du WW, Ouyang YQ. Efficacy and safety of domperidone and metoclopramide in breastfeeding: a systematic review and meta-analysis. Breastfeed Med. 2021;16(7):516-529.
- Si S, Zhao G, Song G, Liu J. Efficacy and safety of domperidone and metoclopramide on human milk production in postpartum mothers: a Bayesian network meta-analysis of randomized controlled trials. BMC Pregnancy Childbirth. 2024;24:819. doi:10.1186/s12884-024-07027-4.
- U.S. Food and Drug Administration. Information about domperidone [Internet]. 2023.
- Abou-Dakn, M., Fluhr, J. W., Gensch, M., & Wöckel, A. (2011). Positive effect of HPA lanolin versus expressed breastmilk on painful anddamaged nipples during lactation. Skin Pharmacology and Physiology, 24(1), 27–35.
- Ballard, J. L., Auer, C. E., & Khoury, J. C. (2002). Ankyloglossia: assessment, incidence, and effect of frenuloplasty on the breastfeeding dyad. Pediatrics, 110(5), e63.
- Berens P, Eglash A, Malloy M, Steube AM; Academy of Breastfeeding Medicine. ABM Clinical Protocol #26: Persistent pain with breastfeeding. Breastfeed Med. 2016;11(2):46-53. doi:10.1089/bfm.2016.29002.pjb
- Brent, N., Rudy, S. J., Redd, B., Rudy, T. E., & Roth, L. A. (1998). Sore nipples in breast-feeding women: a clinical trial of wound dressings vs conventional care. Archives of Pediatrics & Adolescent Medicine, 152(11), 1077–1082.
- Dennis, C.-L., Jackson, K., & Watson, J. (2014). Interventions for treating painful nipples among breastfeeding women. Cochrane Database of Systematic Reviews, (12), CD007366.
- Dennis, C.-L., Schottle, N., Hodnett, E., & McQueen, K. (2012). An all-purpose nipple ointment versus lanolin in treating painful damaged nipples in breastfeeding women : a randomized controlled trial. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 7(6), 473–479.
- Dodd, V., & Chalmers, C. (2003). Comparing the use of hydrogel dressings to lanolin ointment with lactating mothers. Journal of Obstetric, Gynecologic, and Neonatal Nursing: JOGNN, 32(4), 486–494.
- Gungor, A. N. C., Oguz, S., Vurur, G., Gencer, M., Uysal, A., Hacivelioglu, S., Cosar, E. (2013). Comparison of olive oil and lanolin in the prevention of sore nipples in nursing mothers. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 8(3), 334–335.
- Jackson, K. T., & Dennis, C.-L. (2017). Lanolin for the treatment of nipple pain in breastfeeding women : a randomized controlled trial. Maternal & Child Nutrition, 13(3). Doi :10.1111/mcn.12357
- Kent, J. C., Ashton, E., Hardwick, C. M., Rowan, M. K., Chia, E. S., Fairclough, K. A., Geddes, D. T. (2015). Nipple pain in breastfeeding mothers : Incidence, causes and treatments. International Journal of Environmental Research and Public Health, 12(10), 12247–12263.
- Mariani Neto, C., de Albuquerque, R. S., de Souza, S. C., Giesta, R. O., Fernandes, A. P. S., & Mondin, B. (2018). Comparative study of the use of HPA lanolin and breast milk for treating pain associated with nipple trauma. Revista Brasileira de Ginecologia e Obstetricia: Revista Da Federacao Brasileira Das Sociedades de Ginecologia e Obstetricia, 40(11), 664–672.
- Melli, M. S., Rashidi, M.-R., Nokhoodchi, A., Tagavi, S., Farzadi, L., Sadaghat, K., Sheshvan, M. K. (2007). A randomized trial of peppermint gel, lanolin ointment, and placebo gel to prevent nipple crack in primiparous breastfeeding women. Medical Science Monitor: International Medical Journal of Experimental and Clinical Research, 13(9), CR406-411.
- Mohammadzadeh, A., Farhat, A., & Esmaeily, H. (2005). The effect of breast milk and lanolin on sore nipples. Saudi Medical Journal, 26(8), 1231–1234.
- Morland-Schultz, K., & Hill, P. D. (2005). Prevention of and therapies for nipple pain : à systematic review. Journal of Obstetric, Gynecologic, and Neonatal Nursing: JOGNN, 34(4), 428–437.
- Nakamura M, Koyama M, Sakaguchi S, Kido A, Matsuzaki M, Murakami K. Systematic review on the efficacy of moisturizing therapy for nipple trauma and pain in lactating women. J Hum Lact. 2025. doi:10.1177/08903344241301401
- Niazi, A., Yousefzadeh, S., Rakhshandeh, H., Esmaily, H., & Askari, V. R. (2019). Promising effects of purslane cream on the breast fissure in lactating women : A clinical trial. Complementary Therapies in Medicine, 43, 300–305.
- Nozimoto INP, da Silva FCB, Rocha IM, Coca KP, de Abreu LC, Bueno KCV, et al. Nonpharmacological interventions for treating breastfeeding nipple pain: systematic review and meta-analysis. Breastfeed Med. 2024;19(8):617-629. doi:10.1089/bfm.2024.0043
- Pugh, L. C., Buchko, B. L., Bishop, B. A., Cochran, J. F., Smith, L. R., & Lerew, D. J. (1996). A comparison of topical agents to relieve nipple pain and enhance breastfeeding. Birth (Berkeley, Calif.), 23(2), 88–93.
- Righard, L., & Alade, M. O. (1992). Sucking technique and its effect on success of breastfeeding. Birth (Berkeley, Calif.), 19(4), 185–189.
- Scolnik D, Glatstein M. Lanolin for nipple pain in breastfeeding mothers. Am J Ther. 2017;24(4):e500-e501. doi:10.1097/MJT.0000000000000489.
- Shanazi, M., Farshbaf Khalili, A., Kamalifard, M., Asghari Jafarabadi, M., Masoudin, K., & Esmaeli, F. (2015). Comparison of the effects of lanolin, peppermint, and dexpanthenol creams on treatment of traumatic nipples in breastfeeding mothers. Journal of Caring Sciences, 4(4), 297–307.
- Valdová V, Štěpánová V, Lapčíková L. The safety and efficacy of neutral electrolyzed water solution for wound irrigation: post-market clinical follow-up study. Front Drug Saf Regul. 2025;4:1402684. doi:10.3389/fdsfr.2024.1402684.
- Vieira, F., Bachion, M. M., Mota, D. D. C. F., & Munari, D. B. (2013). A systematic review of the interventions for nipple trauma in breastfeeding mothers : Interventions for nipple trauma. Journal of Nursing Scholarship, 45(2), 116–125.
- Vieira, F., Mota, D. D. C. F., Castral, T. C., Guimarães, J. V., Salge, A. K. M., & Bachion, M. M. (2017). Effects of anhydrous lanolin versus breast milk combined with a breast shell for the treatment of nipple trauma and pain during breastfeeding : A randomized clinical trial. Journal of Midwifery & Women’s Health, 62(5), 572–579.
- Żukowska-Rubik M, Nehring-Gugulska M, Mrozikiewicz-Rakowska B, Aleksy-Polipowska M, Żółtowska N, Kulińska R, et al. Treatment of nipple wounds during breastfeeding. Position of the Center for Lactation Science and the Polish Wound Management Association. Leczenie Ran. 2025;22(2):46-79. doi:10.60075/lr.v22i2.103.
- Amir LH, Pirotta MV, Raval M. Breastfeeding—evidence based guidelines for the use of medicines. Aust Fam Physician. 2011;40(9):684-690. PMID: 21894275.
- Anderson, P. O. (2017). Herbal use during breastfeeding. Breastfeeding medicine: the official journal of the Academy of Breastfeeding Medicine, 12(9), 507–509.
- Badgujar, S. B., Patel, V. V., & Bandivdekar, A. H. (2014). Foeniculum vulgare Mill : a review of its botany, phytochemistry, pharmacology, contemporary application, and toxicology. BioMed Research International, 2014, 842674.
- Bakerink, J. A., Gospe, S. M., Jr, Dimand, R. J., & Eldridge, M. W. (1996). Multiple organ failure after ingestion of pennyroyal oil from herbal tea in two infants. Pediatrics, 98(5), 944–947.
- Bakkali, F., Averbeck, S., Averbeck, D., & Idaomar, M. (2008). Biological effects of essential oils--a review. Food and Chemical Toxicology : An International Journal Published for the British Industrial Biological Research Association, 46(2), 446–475.
- Blumenthal, M. (1998). The American Botanical Council. The Complete German Commission E Monographs: Therapeutic Guide to Herbal Medicines. Ed. Integrative Medicine Com. Boston.
- Budzynska, K., Gardner, Z. E., Dugoua, J.-J., Low Dog, T., & Gardiner, P. (2012). Systematic review of breastfeeding and herbs. Breastfeeding Medicine : The Official Journal of the Academy of Breastfeeding Medicine, 7(6), 489–503.
- Bunchorntavakul, C., & Reddy, K. R. (2013). Review article : herbal and dietary supplement hepatotoxicity. Alimentary Pharmacology & Therapeutics, 37(1), 3–17.
- Casanova Cuenca, M., Calzado Agrasot, M. Á., Mir Pegueroles, C., & Esteban Cantó, V. (2019). Persisten las intoxicaciones por anís estrellado, ¿estamos dando la suficiente información? Neurología (English Edition), 34(3), 211–213.
- Chan, E. (1993). Displacement of bilirubin from albumin by berberine. Biology of the Neonate, 63(4), 201–208.
- De Boer, H. J., & Cotingting, C. (2014). Medicinal plants for women’s healthcare in southeast Asia : a meta-analysis of their traditional use, chemical constituents, and pharmacology. Journal of Ethnopharmacology, 151(2), 747–767.
- De Groot, A. C., & Schmidt, E. (2016). Essential oils, part III : Chemical composition. Dermatitis : Contact, Atopic, Occupational, Drug: Official Journal of the American Contact Dermatitis Society, North American Contact Dermatitis Group, 27(4), 161–169.
- Denzer, M. Y., Kirsch, F., & Buettner, A. (2015). Are odorant constituents of herbal tea transferred into human milk ? Journal of Agricultural and Food Chemistry, 63(1), 104–111.
- Deutch, M. R., Grimm, D., Wehland, M., Infanger, M., & Krüger, M. (2019). Bioactive candy : Effects of licorice on the cardiovascular system. Foods (Basel, Switzerland), 8(10), 495.
- Dosoky, N. S., & Setzer, W. N. (2021). Maternal reproductive toxicity of some essential oils and their constituents. International Journal of Molecular Sciences, 22(5), 2380.
- Efferth, T., & Kaina, B. (2011). Toxicities by herbal medicines with emphasis to traditional Chinese medicine. Current Drug Metabolism, 12(10), 989–996.
- Eglash, A. (2014). Treatment of maternal hypergalactia. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 9(9), 423–425.
- Europa Press. Sanidad retira cautelarmente los anises para bebés tras detectar efectos adversos en 20 niños. El Mundo.es, 27.10.20012001
- Farrar, A. J., & Farrar, F. C. (2020). Clinical aromatherapy. The Nursing Clinics of North America, 55(4), 489–504.
- FDA warns consumers about star anise teas. FDA Consum. 2003 Nov-Dec;37(6):4.
- Flores-Robles, B. J., Sandoval, A. R. H., Dardon, J. D. P., & Blas, C. A. (2013). Lethal liquorice lollies (liquorice abuse causing pseudohyperaldosteronism). BMJ Case Reports, 2013(sep19 1), bcr2013201007–bcr2013201007.
- Foong, S. C., Tan, M. L., Foong, W. C., Marasco, L. A., Ho, J. J., & Ong, J. H. (2020). Oral galactagogues (natural therapies or drugs) for increasing breast milk production in mothers of non-hospitalised term infants. Cochrane Database of Systematic Reviews, 5, CD011505.
- Gil Campos, M., Pérez Navero, J. L., & Ibarra De La Rosa, I. (2002). Convulsive status secondary to star anise poisoning in a neonate. Anales espanoles de pediatria, 57(4), 366–368.
- Gordon, M., Biagioli, E., Sorrenti, M., Lingua, C., Moja, L., Banks, S. S., … Savino, F. (2018). Dietary modifications for infantile colic. Cochrane Database of Systematic Reviews, 10(2), CD011029.
- Harb, T., Matsuyama, M., David, M., & Hill, R. J. (2016). Infant colic-what works : A systematic review of interventions for breast-fed infants. Journal of Pediatric Gastroenterology and Nutrition, 62(5), 668–686.
- Hardy, M. L. (2000). Herbs of special interest to women. Journal of the American Pharmaceutical Association (Washington, D.C.: 1996), 40(2), 234–242; quiz 327–329.
- Hausner H, Bredie WLP, Mølgaard C, Petersen MA, Møller P. Differential transfer of dietary flavour compounds into human breast milk. Physiol Behav. 2008;95(1-2):118-124. doi:10.1016/j.physbeh.2008.05.007. PMID: 1857120.
- Ize-Ludlow, D. (2004). Neurotoxicities in infants seen with the consumption of star anise tea. Pediatrics, 114(5), e653–e656.
- Johanns, E. S. D., van der Kolk, L. E., van Gemert, H. M. A., Sijben, A. E. J., Peters, P. W. J., & de Vries, I. (2002). An epidemic of epileptic seizures after consumption of herbal tea. Nederlands tijdschrift voor geneeskunde, 146(17), 813–816.
- Kaygusuz, M., Gümüştakım, R. Ş., Kuş, C., İpek, S., & Tok, A. (2021). TCM use in pregnant women and nursing mothers : A study from Turkey. Complementary Therapies in Clinical Practice, 42(101300), 101300.
- Kim, J.-H., Jung, S.-H., Yang, Y.-I., Ahn, J.-H., Cho, J.-G., Lee, K.-T., … Choi, J.-H. (2013). Artemisia leaf extract induces apoptosis in human endometriotic cells through regulation of the p38 and NFκB pathways. Journal of Ethnopharmacology, 145(3), 767–775.
- Lawrence RA, Lawrence RM. Breastfeeding: A Guide for the Medical Profession. 7th ed. Maryland Heights, MO: Mosby/Elsevier; 2011. ISBN: 9781437707885.
- Le Moli, R., Endert, E., Fliers, E., Mulder, T., Prummel, M. F., Romijn, J. A., & Wiersinga, W. M. (1999). Establishment of reference values for endocrine tests. II : Hyperprolactinemia. The Netherlands Journal of Medicine, 55(2), 71–75.
- Leach, M. J., & Moore, V. (2012). Black cohosh (Cimicifuga spp.) for menopausal symptoms. Cochrane Database of Systematic Reviews, (9), CD007244.
- Madden, G. R., Schmitz, K. H., & Fullerton, K. (2012). A case of infantile star anise toxicity. Pediatric Emergency Care, 28(3), 284–285.
- Mathon, C., Bongard, B., Duret, M., Ortelli, D., Christen, P., & Bieri, S. (2013). Analysis of the neurotoxin anisatin in star anise by LC-MS/MS. Food Additives & Contaminants. Part A, Chemistry, Analysis, Control, Exposure & Risk Assessment, 30(9), 1598–1605.
- Minodier, P., Pommier, P., Moulène, E., Retornaz, K., Prost, N., & Deharo, L. (2003). Intoxication aiguë par la badiane chez le nourrisson. [Star anise poisoning in infants. Archives de pediatrie : organe officiel de la Societe francaise de pediatrie, 10(7), 619–621.
- Moro, P. A., Flacco, V., Cassetti, F., Clementi, V., Colombo, M. L., Chiesa, G. M., Santuccio, C. (2011). Hypovolemic shock due to severe gastrointestinal bleeding in a child taking an herbal syrup. Annali Dell’Istituto Superiore Di Sanita, 47(3), 278–283.
- MSC - Ministerio de Sanidad y Consumo de España. ORDEN SCO/190/2004, de 28 de enero, por la que se establece la lista de plantas cuya venta al público queda prohibida o restringida por razón de su toxicidad.BOE 2004; 32:5061-6065
- Obando Pacheco, P., Martínez-Martínez, P. L., Pérez de Eulate Bazán, Y., de la Mota Ybancos, J. L., Milano Manso, G., & Sierra Salinas, C. (2016). Liver failure secondary to poisoning by a homemade product made of star and green anise in a 4-month-old infant. Revista Espanola de Enfermedades Digestivas: Organo Oficial de La Sociedad Espanola de Patologia Digestiva, 108(12), 819–821.
- Panduranga, P., & Al-Rawahi, N. (2013). Licorice-induced severe hypokalemia with recurrent torsade de pointes: Licorice-induced severe hypokalemia. Annals of Noninvasive Electrocardiology : The Official Journal of the International Society for Holter and Noninvasive Electrocardiology, Inc, 18(6), 593–596.
- Penninkilampi, R., Eslick, E. M., & Eslick, G. D. (2017). The association between consistent licorice ingestion, hypertension and hypokalaemia: a systematic review and meta-analysis. Journal of Human Hypertension, 31(11), 699–707.
- Perret, C., Tabin, R., Marcoz, J.-P., Llor, J., & Cheseaux, J.-J. (2011). Malaise du nourrisson pensez à une intoxication à l’anis étoilé. Archives de pediatrie: organe officiel de la Societe francaise de pediatrie, 18(7), 750–753.
- Posadzki, P., Watson, L., & Ernst, E. (2013). Contamination and adulteration of herbal medicinal products (HMPs) : an overview of systematic reviews. European Journal of Clinical Pharmacology, 69(3), 295–307.
- Powers, C. N., & Setzer, W. N. (2015). A molecular docking study of phytochemical estrogen mimics from dietary herbal supplements. In Silico Pharmacology, 3(1), 4.
- Rad, S. Z. K., Rameshrad, M., & Hosseinzadeh, H. (2017). Toxicology effects of Berberis vulgaris (barberry) and its active constituent, berberine : a review. Iranian Journal of Basic Medical Sciences, 20(5), 516–529.
- Reis, D., & Jones, T. (2017). Aromatherapy : Using essential oils as a supportive therapy. Clinical Journal of Oncology Nursing, 21(1), 16–19.
- Rosti L, Nardini A, Bettinelli ME, Rosti D. Toxic effects of a herbal tea mixture in two newborns. Acta Paediatr. 1994;83(6):683. doi:10.1111/j.1651-2227.1994.tb13115.x. PMID: 7919774.
- Sibeko, L., & Johns, T. (2021). Global survey of medicinal plants during lactation and postpartum recovery : Evolutionary perspectives and contemporary health implications. Journal of Ethnopharmacology, 270(113812), 113812.
- Siegel, R. K. (1976). Herbal intoxication. Psychoactive effects from herbal cigarettes, tea, and capsules. JAMA: The Journal of the American Medical Association, 236(5), 473–476.
- Skidmore-Roth, L. (2011). Mosby’s handbook of herbs & natural supplements - (4a ed.). Londres, Inglaterra: Mosby.
- Techen, N., Pan, Z., Scheffler, B., & Khan, I. (2009). Detection ofIllicium anisatumas Adulterant ofIllicium verum. Planta Medica, 75(04), 392–395. Hausner, H., Bredie, W. L. P., Mølgaard, C., Petersen, M. A., & Møller, P. (2008). Differential transfer of dietary flavour compounds into human breast milk. Physiology & Behavior, 95(1–2), 118–124.
- Türkyilmaz, Z., Karabulut, R., Sönmez, K., & Can Başaklar, A. (2008). A striking and frequent cause of premature thelarche in children : Foeniculum vulgare. Journal of Pediatric Surgery, 43(11), 2109–2111.
- U.S. Food and Drug Administration. Information for consumers on using dietary supplements [Internet]. Silver Spring (MD): FDA; 2022.
- U.S. Food and Drug Administration. Center for Food Safety and Applied Nutrition 2003: star anise teas advisory[Internet]. Silver Spring (MD): FDA; 2003.
- Usta, C., Tanyeri-Bayraktar, B., & Bayraktar, S. (2021). Pain control with lavender oil in premature infants : A double-blind randomized controlled study. Journal of Alternative and Complementary Medicine (New York, N.Y.), 27(2), 136–141.
- Vanaclocha B, Cañigueral S, eds. Monografía de [nombre de la planta]. Fitoterapia, Vademécum de Prescripción [Internet]. Carlet: Cita Publicaciones y Documentación; [consultado 2026 abr 28]. Disponible en: URL de la ficha.
- Vandenberghe, N., Pittion-Vouyouvitch, S., Flesch, F., Wagner, M., & Godet, E. (2003). An inaugural generalized tonic-clonic convulsive crisis following ingestion of Japanese star anise. Presse medicale (Paris, France : 1983), 32(1), 27–28.
- Vigan, M. (2010). Essential oils : renewal of interest and toxicity. European Journal of Dermatology: EJD, 20(6), 685–692.
- Wagner, C. L., Boan, A. D., Marzolf, A., Finch, C. W., Morella, K., Guille, C., Marriott, B. P. (2019). The safety of Mother’s Milk® tea: Results of a randomized double-blind, controlled study in fully breastfeeding mothers and their infants. Journal of Human Lactation : Official Journal of International Lactation Consultant Association, 35(2), 248–260.
- Werner, S., Brismar, K., & Olsson, S. (1979). Hyperprolactinæmia and liquorice. Lancet, 313(8111), 319.
- WHO monographs on selected medicinal plants - volume 4. (s/f). Recuperado el 27 de septiembre de 2021, de Digicollection.org website: http Chan, E. (1993). Displacement of bilirubin from albumin by berberine. Biology of the Neonate, 63(4), 201–208.
- Zhou, S., Koh, H.-L., Gao, Y., Gong, Z.-Y., & Lee, E. J. D. (2004). Herbal bioactivation : the good, the bad and the ugly. Life Sciences, 74(8), 935–968.
- Academy of Breastfeeding Medicine. (2011). ABM clinical protocol #24: Allergic proctocolitis in the exclusively breastfed infant. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 6(6), 435–440.
- Amorim Adegboye, A. R., & Linne, Y. M. (2013). Diet or exercise, or both, for weight reduction in women after childbirth. Cochrane Database of Systematic Reviews, (7), CD005627.
- Ares Segura, S., Arena Ansótegui, J., Díaz-Gómez, N. M., & en representación del Comité de Lactancia Materna de la Asociación Española de Pediatría. (2016). La importancia de la nutrición materna durante la lactancia, ¿necesitan las madres lactantes suplementos nutricionales? Anales de pediatria (Barcelona, Spain: 2003), 84(6), 347.e1-7.
- Bener, A., Ehlayel, M. S., Alsowaidi, S., & Sabbah, A. (2007). Role of breast feeding in primary prevention of asthma and allergic diseases in a traditional society. European Annals of Allergy and Clinical Immunology, 39(10), 337–343.
- Blanchard, J., Weber, C. W., & Shearer, L. E. (1992). Methylxanthine levels in breast milk of lactating women of different ethnic and socioeconomic classes. Biopharmaceutics & Drug Disposition, 13(3), 187–196.
- Borak, J. (2005). Neonatal hypothyroidism due to maternal vegan diet. Journal of Pediatric Endocrinology & Metabolism, 18(6), 621.
- Bordini, C. A., Roesler, C., Carvalho, D. de S., Macedo, D. D. P., Piovesan, É., Melhado, E. M., … Vincent, M. B. (2016). Recommendations for the treatment of migraine attacks - a Brazilian consensus. Arquivos de Neuro-Psiquiatria, 74(3), 262–271.
- Bravi, F., Di Maso, M., Eussen, S. R. B. M., Agostoni, C., Salvatori, G., Profeti, C., On Behalf Of The Medidiet Working Group. (2021). Dietary patterns of breastfeeding mothers and human milk composition : Data from the Italian MEDIDIET study. Nutrients, 13(5), 1722.
- Briggs GG, Freeman RK, Towers CV, Forinash AB. Drugs in Pregnancy and Lactation: A Reference Guide to Fetal and Neonatal Risk. 11th ed. Philadelphia: Wolters Kluwer; 2017. ISBN: 9781496349620.
- Brzezińska, M., Kucharska, A., & Sińska, B. (2016). Vegetarian diets in the nutrition of pregnant and breastfeeding women. Polski merkuriusz lekarski: organ Polskiego Towarzystwa Lekarskiego, 40(238), 264–268.
- Butte, N. F., Garza, C., Stuff, J. E., Smith, E. O., & Nichols, B. L. (1984). Effect of maternal diet and body composition on lactational performance. The American Journal of Clinical Nutrition, 39(2), 296–306.
- Butte, Nancy F., & King, J. C. (2005). Energy requirements during pregnancy and lactation. Public Health Nutrition, 8(7A), 1010–1027.
- Bzikowska, A., Czerwonogrodzka-Senczyna, A., Wesołowska, A., & Weker, H. (2017). Nutrition during breastfeeding - impact on human milk composition. Polski Merkuriusz Lekarski: Organ Polskiego Towarzystwa Lekarskiego, 43(258), 276–280.
- Calvaresi, V., Escuder, D., Minutillo, A., Bastons-Compta, A., García-Algar, O., Pallás Alonso, C. R., … Pichini, S. (2016). Transfer of nicotine, cotinine, and caffeine into breast milk in a smoker mother consuming caffeinated drinks. Journal of Analytical Toxicology, 40(6), 473–477.
- Centers for Disease Control and Prevention (CDC). (2003). Neurologic impairment in children associated with maternal dietary deficiency of cobalamin--Georgia, 2001. MMWR. Morbidity and Mortality Weekly Report, 52(4), 61–64.
- Davanzo R, Bua J, Paloni G, Facchina G. Breastfeeding and migraine drugs. Eur J Clin Pharmacol. 2014;70(11):1313-1324. doi:10.1007/s00228-014-1748-0. PMID: 25217187.
- Dewey, K. G. (1998). Effects of maternal caloric restriction and exercise during lactation. The Journal of Nutrition, 128(2 Suppl), 386S-389S.
- European Food Safety Authority (EFSA). Scientific Opinion on the safety of caffeine. EFSA J. 2015;13(5):4102.
- Elbert, N. J., van Meel, E. R., den Dekker, H. T., de Jong, N. W., Nijsten, T. E. C., Jaddoe, V. W. V., … Duijts, L. (2017). Duration and exclusiveness of breastfeeding and risk of childhood atopic diseases. Allergy, 72(12), 1936–1943.
- Erdeve, O., Arsan, S., Atasay, B., Ileri, T., & Uysal, Z. (2009). A breast-fed newborn with megaloblastic anemia-treated with the vitamin B12 supplementation of the mother. Journal of Pediatric Hematology/Oncology, 31(10), 763–765.
- González Reyes, A. B., Hardisson de la Torre, A., Gutiérrez Fernández, A. J., Rubio Armendáriz, C., Frías Tejera, I., & Revert Gironés, C. (2015). Caffeine and quinine in soft drinks ; Contribution to the dietary intake. Nutricion hospitalaria: organo oficial de la Sociedad Espanola de Nutricion Parenteral y Enteral, 32(6), 2880–2886.
- Guez, S., Chiarelli, G., Menni, F., Salera, S., Principi, N., & Esposito, S. (2012). Severe vitamin B12 deficiency in an exclusively breastfed 5-month-old Italian infant born to a mother receiving multivitamin supplementation during pregnancy. BMC Pediatrics, 12(1), 85.
- Hale TW. Hale’s Medications & Mothers’ Milk 2019: A Manual of Lactational Pharmacology. 18th ed. New York: Springer Publishing Company; 2018. ISBN: 9780826135582.
- Jeurink, P. V., Knipping, K., Wiens, F., Barańska, K., Stahl, B., Garssen, J., & Krolak-Olejnik, B. (2019). Importance of maternal diet in the training of the infant’s immune system during gestation and lactation. Critical Reviews in Food Science and Nutrition, 59(8), 1311–1319.
- Keikha, M., Bahreynian, M., Saleki, M., & Kelishadi, R. (2017). Macro- and micronutrients of human milk composition : Are they related to maternal diet? A comprehensive systematic review. Breastfeeding medicine: the official journal of the Academy of Breastfeeding Medicine, 12(9), 517–527.
- Kocaoglu, C., Akin, F., Caksen, H., Böke, S. B., Arslan, S., & Aygün, S. (2014). Cerebral atrophy in a vitamin B12-deficient infant of a vegetarian mother. Journal of Health, Population, and Nutrition, 32(2), 367–371.
- Lawrence RA, Lawrence RM. Breastfeeding: A Guide for the Medical Profession. 7th ed. Maryland Heights, MO: Mosby/Elsevier; 2011. ISBN: 9781437707885.
- López-Olmedo, N., Hernández-Cordero, S., Neufeld, L. M., García-Guerra, A., Mejía-Rodríguez, F., & Méndez Gómez-Humarán, I. (2016). The associations of maternal weight change with breastfeeding, diet, and physical activity during the postpartum period. Maternal and Child Health Journal, 20(2), 270–280.
- Mariani, A., Chalies, S., Jeziorski, E., Ludwig, C., Lalande, M., & Rodière, M. (2009). Conséquences de l’allaitement maternel exclusif chez le nouveau-né de mère végétalienne – À propos d’un cas. Archives de pediatrie : organe officiel de la Societe francaise de pediatrie, 16(11), 1461–1463.
- McCreedy, A., Bird, S., Brown, L. J., Shaw-Stewart, J., & Chen, Y.-F. (2018). Effects of maternal caffeine consumption on the breastfed child : a systematic review. Swiss Medical Weekly, 148, w14665.
- McCrory, M. A., Nommsen-Rivers, L. A., Molé, P. A., Lönnerdal, B., & Dewey, K. G. (1999). Randomized trial of the short-term effects of dieting compared with dieting plus aerobic exercise on lactation performance. The American Journal of Clinical Nutrition, 69(5), 959–967.
- McGuinness, N., & Cording, V. (2013). Raynaud’s phenomenon of the nipple associated with labetalol use. Journal of Human Lactation : Official Journal of International Lactation Consultant Association, 29(1), 17–19.
- McNamara, P. J., & Abbassi, M. (2004). Neonatal exposure to drugs in breast milk. Pharmaceutical Research, 21(4), 555–566.
- Melina, V., Craig, W., & Levin, S. (2016). Position of the Academy of Nutrition and Dietetics : Vegetarian diets. Journal of the Academy of Nutrition and Dietetics, 116(12), 1970–1980.
- Mitchell, J. L. (1999). Use of cough and cold preparations during breastfeeding. Journal of Human Lactation : Official Journal of International Lactation Consultant Association, 15(4), 347–349.
- Muñoz, L. M., Lönnerdal, B., Keen, C. L., & Dewey, K. G. (1988). Coffee consumption as a factor in iron deficiency anemia among pregnant women and their infants in Costa Rica. The American Journal of Clinical Nutrition, 48(3), 645–651.
- Nerveen, R.J.J.V y Salvelkoul H. (2017). Nutrition and Allergic Diseases. Nutrients, 9 (7).
- Neville, C. E., McKinley, M. C., Holmes, V. A., Spence, D., & Woodside, J. V. (2014). The relationship between breastfeeding and postpartum weight change--a systematic review and critical evaluation. International Journal of Obesity (2005) , 38(4), 577–590.
- Norén, K. (1983). Levels of organochlorine contaminants in human milk in relation to the dietary habits of the mothers. Acta Paediatrica (Oslo, Norway: 1992), 72(6), 811–816.
- Oddy, W. H. (2017). Breastfeeding, childhood asthma, and allergic disease. Annals of Nutrition & Metabolism, 70 Suppl 2(Suppl. 2), 26–36.
- Paricio Talayero JM. El libro de la lactancia: todo lo que las madres y la ciencia nos han enseñado sobre la lactancia. Barcelona: Penguin Random House; 2020. ISBN: 978-84-16076-83-3.
- Roed, C., Skovby, F., & Lund, A. M. (2009). Severe vitamin B12 deficiency in infants breastfed by vegans. Ugeskrift for laeger, 171(43), 3099–3101.
- Rowe H, Baker T, Hale TW. Maternal medication, drug use, and breastfeeding. Pediatr Clin North Am. 2013;60(1):275-294. doi:10.1016/j.pcl.2012.10.009. PMID: 23178070.
- Ryu, J. E. (1985). Effect of maternal caffeine consumption on heart rate and sleep time of breast-fed infants. Developmental Pharmacology and Therapeutics, 8(6), 355–363.
- Sámano, R., Martínez-Rojano, H., Godínez Martínez, E., Sánchez Jiménez, B., Villeda Rodríguez, G. P., Pérez Zamora, J., & Casanueva, E. (2013). Effects of breastfeeding on weight loss and recovery of pregestational weight in adolescent and adult mothers. Food and Nutrition Bulletin, 34(2), 123–130.
- Sanders, T. A. B. (2009). DHA status of vegetarians. Prostaglandins, Leukotrienes, and Essential Fatty Acids, 81(2–3), 137–141.
- Santos, I. S., Matijasevich, A., & Domingues, M. R. (2012). Maternal caffeine consumption and infant nighttime waking : prospective cohort study. Pediatrics, 129(5), 860–868.
- Schalla, S., Witcomb, G., & Haycraft, E. (2017). Body shape and weight loss as motivators for breastfeeding initiation and continuation. International Journal of Environmental Research and Public Health, 14(7), 754.
- Shaikh, M. G., Anderson, J. M., Hall, S. K., & Jackson, M. A. (2003). Transient neonatal hypothyroidism due to a maternal vegan diet. Journal of Pediatric Endocrinology & Metabolism, 16(1), 111–113.
- Specker, B. L., Black, A., Allen, L., & Morrow, F. (1990). Vitamin B-12 : low milk concentrations are related to low serum concentrations in vegetarian women and to methylmalonic aciduria in their infants. The American Journal of Clinical Nutrition, 52(6), 1073–1076.
- Taylor, S. N. (2018). ABM clinical protocol #29: Iron, zinc, and vitamin D supplementation during breastfeeding. Breastfeeding Medicine: The Official Journal of the Academy of Breastfeeding Medicine, 13(6), 398–404.
- Tian, H.-M., Wu, Y.-X., Lin, Y.-Q., Chen, X.-Y., Yu, M., Lu, T., & Xie, L. (2019). Dietary patterns affect maternal macronutrient intake levels and the fatty acid profile of breast milk in lactating Chinese mothers. Nutrition (Burbank, Los Angeles County, Calif.), 58, 83–88.
- Vandenplas Y, Broekaert I, Domellöf M, Indrio F, Lapillonne A, Pienar C, et al. An ESPGHAN position paper on the diagnosis, management, and prevention of cow’s milk allergy. J Pediatr Gastroenterol Nutr. 2024;78(2):386-413. doi:10.1097/MPG.0000000000003897